As of October 1, 2026 (KST)
We already have once-weekly obesity drugs. So why do Novo Nordisk and Eli Lilly keep exploring technologies that last even longer? Let’s work through the practical reasons: helping patients tolerate treatment, reach a useful dose, and stay on it. Then we’ll look at the deals, release mechanisms, drug losses, and manufacturing challenges.
In this article
Verified Data
Start with a simple idea: the same drug can become a different product if its delivery schedule changes. In the US, injectable Wegovy and Zepbound are once-weekly products. Their active ingredients, semaglutide and tirzepatide, are already designed to remain in the body for a relatively long time. [1, 2]
Two approaches need to stay separate. One makes the drug molecule last longer. The other makes a reservoir under the skin release the drug gradually. Think of a sink: one slows the drain, while the other controls the faucet. The body is more complicated, but separating drug input from removal makes the rest much easier to follow. [1, 16, 17]
There is some evidence that fewer injections can help people stay on treatment. In the US STAY observational study of people with type 2 diabetes, weekly GLP-1 injections were associated with better persistence and adherence than daily injections. This wasn’t a randomized trial, though, and it doesn’t establish the same benefit for monthly obesity drugs. [3]
A quick terminology note: GLP-1, GIP, and amylin identify different signaling targets. A receptor agonist activates the receptor that receives a signal. Dual and triple agonists target multiple receptors. You don’t need to memorize every name. Just keep the drug’s targets separate from the technology used to deliver it over time. [2, 7, 25]
That doesn’t establish that less frequent dosing automatically means higher sales. What we can verify is that both companies have signed or evaluated multiple long-acting technologies. Whether convenience becomes better persistence and a stronger business will depend on the product. [4–9]
The problem patients still face: getting started and staying on treatment
Titration means increasing the dose in steps to help the body adjust. The basic US Wegovy injection schedule spends four weeks each at 0.25, 0.5, 1, and 1.7 mg before maintenance begins in week 17. Zepbound starts at 2.5 mg for four weeks, then moves to 5 mg, with further increases if needed after at least four weeks at the current dose. Both labels link gradual escalation to reducing gastrointestinal side effects. [39, 40]
These schedules illustrate a development challenge, not personal dosing instructions. Wegovy 2.4 mg is the comparison example in this article, not its only maintenance dose or maximum dose. Nor does every Zepbound patient need to reach 15 mg; response and tolerability matter. [39, 40]
Tolerability is about whether someone can live with the side effects and continue treatment. In Zepbound’s approval trials, gastrointestinal reactions caused some patients to stop. Nausea, vomiting, and diarrhea occurred mainly during escalation and declined over time. A drug working and a patient being able to keep taking it are separate questions. [40]
Analysis and Outlook: The Practical Value of Longer-Acting Delivery
The first development goal is to maintain useful drug exposure while avoiding an excessive initial concentration spike. Cmax is the highest concentration in the blood. If controlled release can soften a problematic early peak, developers can test whether that reduces nausea or vomiting while preserving useful exposure. That’s a design hypothesis, not a demonstrated benefit of every monthly formulation. [17, 41]
A lower Cmax alone doesn’t establish better safety. In the FDA’s Wegovy exposure–response review, the proportion reporting gastrointestinal events largely leveled off across the exposure range associated with 2.4 mg; the review identified dose escalation as a possible explanation. Average exposure, the way concentration rises, the escalation schedule, and differences between patients all matter. Lowering the peak by itself has not been shown to guarantee fewer side effects. [41]
The second goal is simpler or faster titration. Fewer dose changes, fewer calendar weeks to maintenance, and fewer injections are three different things. A better release profile might make adjustment easier and allow useful exposure sooner. But putting a month’s supply under the skin doesn’t eliminate titration. A depot that keeps releasing drug can be difficult to adjust midway, making the starting regimen especially important. [33]
An actual development attempt—and its limits
Camurus’ CAM2056 illustrates the idea. In its reported Phase 1b study of 80 adults with overweight or obesity, treatment started with two doses two weeks apart, followed by two monthly doses. Camurus reported similar Cmax and a later peak at four times the weekly dose. More drug per injection needn’t produce a proportionately higher peak. This didn’t demonstrate lower Cmax or superior tolerability. [33]
Camurus suggested faster titration might be possible, but also reported a tendency toward more frequent and severe gastrointestinal events at the highest starting dose. That counterpoint matters. The study had a randomized active-controlled portion and a separate escalation portion; it wasn’t a simultaneous randomized comparison of every dose group establishing that faster initiation was better. [33]
When a patient benefit could become a business benefit
Here’s the business logic. If fewer patients stop or reduce their dose because of side effects, and more reach an effective dose and stay on it, a product could offer more than fewer injections. A better treatment experience could matter even with similar efficacy. But actual weight change, discontinuation, long-term persistence, price, and insurance access still need to be measured. This is an interpretation of the clinical-to-commercial opportunity, not a claim that Novo and Lilly publicly gave these reasons for every deal. [3, 33, 39–41]
Fewer administrations might also reduce the burden of remembering injection days and giving each dose. Products using single-use devices could need fewer devices and packages, although pens differ and implants add a procedure. Additional active ingredient, manufacturing losses, and sterile processing belong in the calculation too. One-quarter as many injections doesn’t mean one-quarter of the cost or four times the supply capacity. [6, 8, 35–38]
On a small screen, swipe the table sideways to read every column.
| Development goal | How clinical and business value might emerge | Evidence actually needed |
|---|---|---|
| Soften an excessive early peak | Preserve efficacy while potentially reducing side effects and discontinuation | GI severity, duration, and discontinuation at comparable effective exposure |
| Simplify or accelerate titration | Reach maintenance sooner or reduce dose-change burden | Time to maintenance, proportion reaching it, discontinuation, and weight change |
| Reduce administrations | Ease daily-life treatment burden and potentially support persistence | Long-term persistence, satisfaction, and weight maintenance in obesity |
| Differentiate the product | Give patients another reason to choose it even if efficacy is similar | Comparisons that include price, insurance access, injection-site reactions, and usability |
| Apply a platform to several candidates | Create more combinations of future molecules and delivery technology | Stability, dose requirements, release, and clinical performance for each molecule |
| Reduce device and packaging burden | Potentially reduce demand for single-use devices | Total costs including API, devices, procedures, and manufacturing yield |
Verified Data: Company Statements and Actual Deals
Let’s separate stated priorities from interpretation. When the TransCon deal was announced in 2024, Novo’s research executive described less frequent treatment as a research focus. Lilly’s Camurus agreement covers up to four compounds across several target classes, giving it room to evaluate delivery technology beyond one product. Buying multiple development options is a reasonable business interpretation—not evidence that every candidate will succeed. Novo’s TransCon collaboration was subsequently the subject of a termination announcement. [4–7]
The deal history shows the direction of interest
Keep licenses, evaluation agreements, and terminations separate. A license grants development or commercialization rights; an evaluation agreement lets a company assess the technology. A deal’s maximum stated value is also different from money already paid. [4, 6, 8, 9]
Milestones are payments triggered by specified development, regulatory, or sales achievements. Royalties are tied to product sales. An upfront payment comes at the beginning of a deal. The maximum possible proceeds and cash already received are different numbers. [4, 6, 9]
On a small screen, swipe the table sideways to read every column.
| Announcement date | Parties and technology | What was announced | What to watch |
|---|---|---|---|
| November 4, 2024 | Novo–Ascendis, TransCon | Lead monthly GLP-1 candidate; up to $285 million in upfront, development, and regulatory payments, plus sales milestones and royalties | Read alongside the later termination announcement. The entire amount wasn’t upfront. [4] |
| June 3, 2025 | Lilly–Camurus, FluidCrystal | Exclusive worldwide rights for up to four Lilly compounds; up to $290 million in upfront, development, and regulatory payments plus $580 million in sales milestones, with royalties separate | The combined $870 million ceiling is conditional. [6] |
| June 1, 2026 | Lilly–Camurus expansion | Exercise of the amylin receptor agonist option triggered an initial $5 million payment | Expansion of the existing agreement, not a fresh $870 million cash payment. [7] |
| July 7, 2026 | Novo–Vivani, NPM-139 | Nonexclusive evaluation agreement for a semaglutide implant | Neither an exclusive commercialization license nor an acquisition. [8] |
| September 14, 2026 | Novo–Ascendis termination announcement | Ascendis announced termination, reversion of rights, and plans for its own development | Don’t assume every legal step finished that day. The release didn’t specify the reason for termination. [5] |
| September 24, 2026 | Novo–Nanexa, PharmaShell | Up to five programs; potential payments totaling up to €1.165 billion | The €615 million component includes upfront, development, and regulatory payments. A separate upfront amount wasn’t disclosed. [9] |
Be especially careful with the inference that Novo ended TransCon and then chose ALD because ALD was better. The announcement dates are verifiable; that causal explanation isn’t. Ascendis said it planned to advance monthly TransCon semaglutide after termination became effective and rights reverted. [5, 9]
Lilly also has an older termination example. On November 8, 2011, it and Amylin announced a mutual end to their exenatide alliance and a settlement of their litigation. Development and commercialization responsibility for Byetta and Bydureon would transfer to Amylin. This belongs to the history of type 2 diabetes, not a recent obesity-drug failure or a verdict against all microspheres. [10, 11]
The technologies extend delivery in different ways
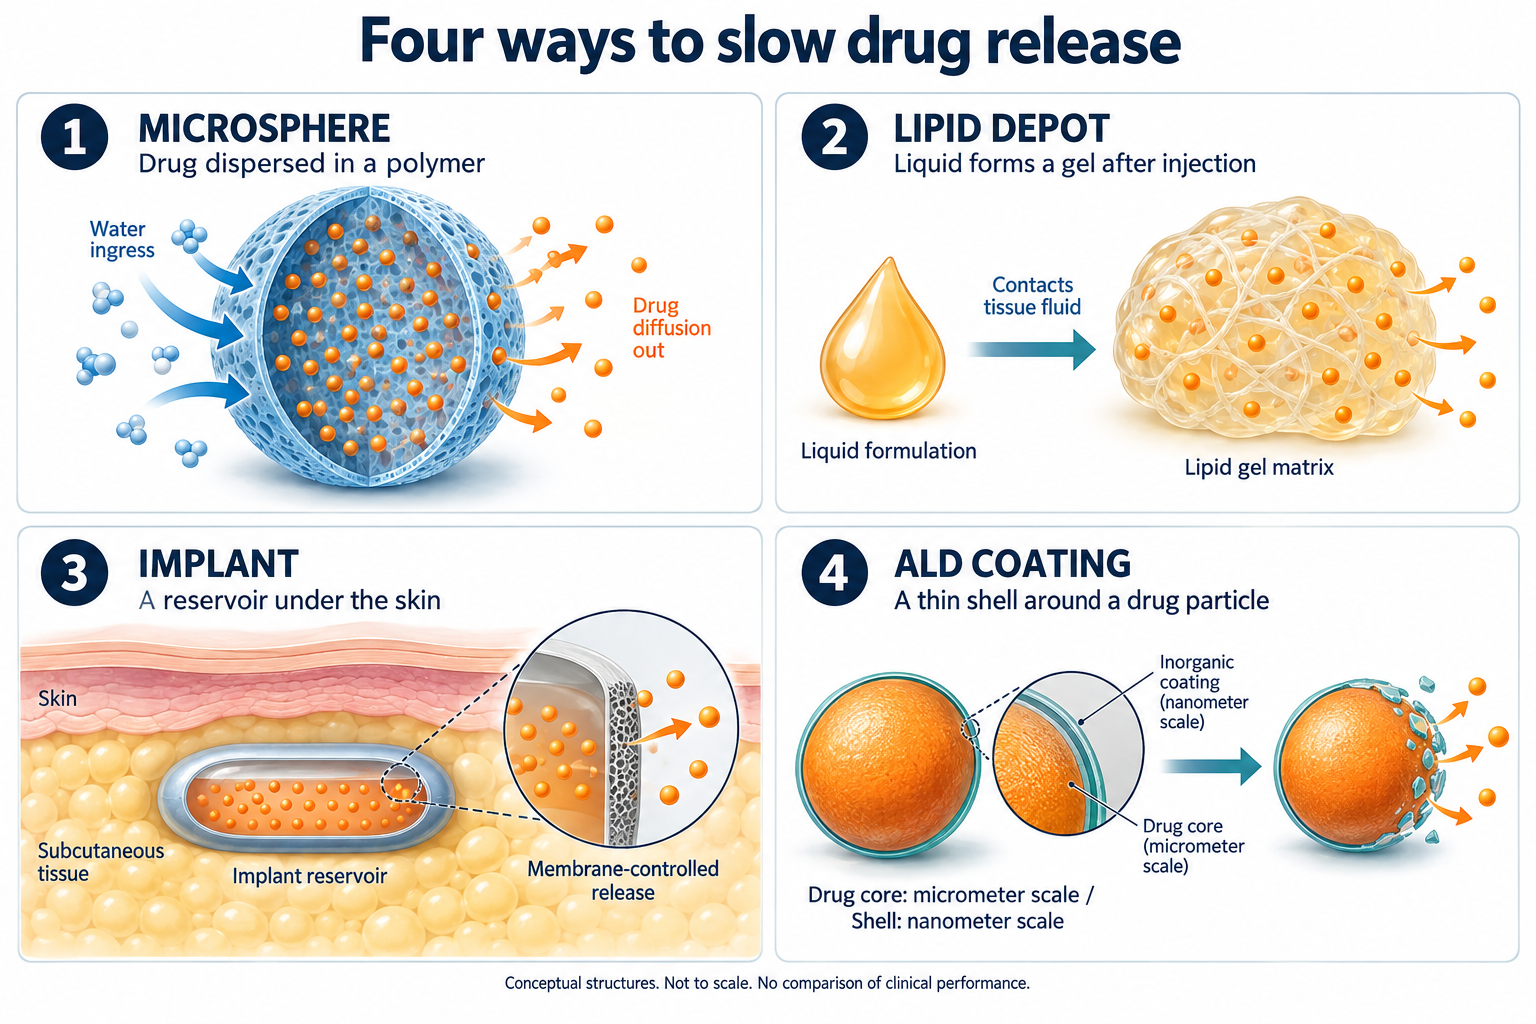
Let’s put pictures to the names. Start with microspheres as tiny polymer beads, lipid depots as gels formed in the body, implants as reservoirs, and ALD as a thin shell around drug particles. The illustration explains structures; it isn’t drawn to scale or a blueprint for a specific product. [8, 12–15]
Microspheres: tiny polymer beads
Microspheres put portions of drug inside tiny biodegradable polymer beads. Water enters, drug diffuses out, and the polymer breaks down. PLGA is one polymer used for this approach. [12, 18]
Bydureon BCise, containing exenatide, is a real example: a weekly microsphere injection approved in the US for type 2 diabetes. It isn’t an example of approved monthly semaglutide for obesity. Experience with a platform doesn’t automatically validate a new ingredient or dosing interval. [12, 18]
Its PK is revealing. After one dose, surface drug releases first; further release as the microspheres hydrate and erode produces a blood concentration peak around weeks 6–7. With weekly dosing, concentrations build for roughly 10 weeks before reaching steady state. A weekly injection doesn’t mean every dose has finished releasing within a week. [12]
Making the beads is only part of the challenge. Polymer properties, manufacturing, storage, and interactions between drug and polymer can affect release. A good-looking laboratory curve still needs to translate into the body. Bydureon’s timetable also shouldn’t be applied to every microsphere product. [12, 18]
Lipid depots: a gel reservoir
Lipid depots take a different route. Camurus describes FluidCrystal as a drug-containing lipid liquid that forms an ordered liquid-crystalline gel when it encounters water in tissue. Drug then leaves this reservoir gradually. [13]
The Lilly–Camurus collaboration aims to apply that technology to Lilly compounds. The companies describe dual and triple agonists and the amylin class, but undisclosed candidates can’t be identified as tirzepatide or any other particular molecule. A gel structure alone doesn’t establish an absence of early burst or better efficacy. [6, 7, 13]
Implants: a reservoir under the skin
An implant places a small reservoir under the skin. Vivani’s NPM-139 is a semaglutide candidate using NanoPortal technology. A removable source is an interesting feature, but convenience has to include insertion and removal. [8]
Implants aren’t interchangeable machines. ITCA 650 used a DUROS osmotic pump: incoming water generated pressure that moved a piston and pushed out exenatide. Describing Vivani’s NanoPortal as having the same internal structure would be wrong. [8, 19]
ALD: a thin coating around drug particles
ALD stands for atomic layer deposition. Nanexa describes PharmaShell as building an extremely thin inorganic coating around microscopic drug particles. The coating’s composition, thickness, and dissolution characteristics are intended to control release. [14, 15]
Compare that with microspheres. A microsphere disperses drug within polymer; ALD coats the drug particle itself. PharmaShell’s micrometer-scale particles have nanometer-scale coatings—the whole particle isn’t necessarily a nanoparticle. The thick-looking shell in the illustration simply makes the distinction visible. [14, 21]
Nanexa highlights the potential to fit a high proportion of drug into the particles and reduce injection volume. It also presents controlled early release and protection of the drug as possible benefits. Actual volume, stability, and release performance need to be established for each substance. A thin coating doesn’t make clinical development automatically easy. [15, 21]
TransCon: a temporary linker and carrier
TransCon connects a drug, a temporary linker, and a carrier. As the linker breaks, the original drug is released. This is a different platform from ALD’s inorganic coating. The next illustration shows the general TransCon concept, not undisclosed structural details of its semaglutide candidate. [16]
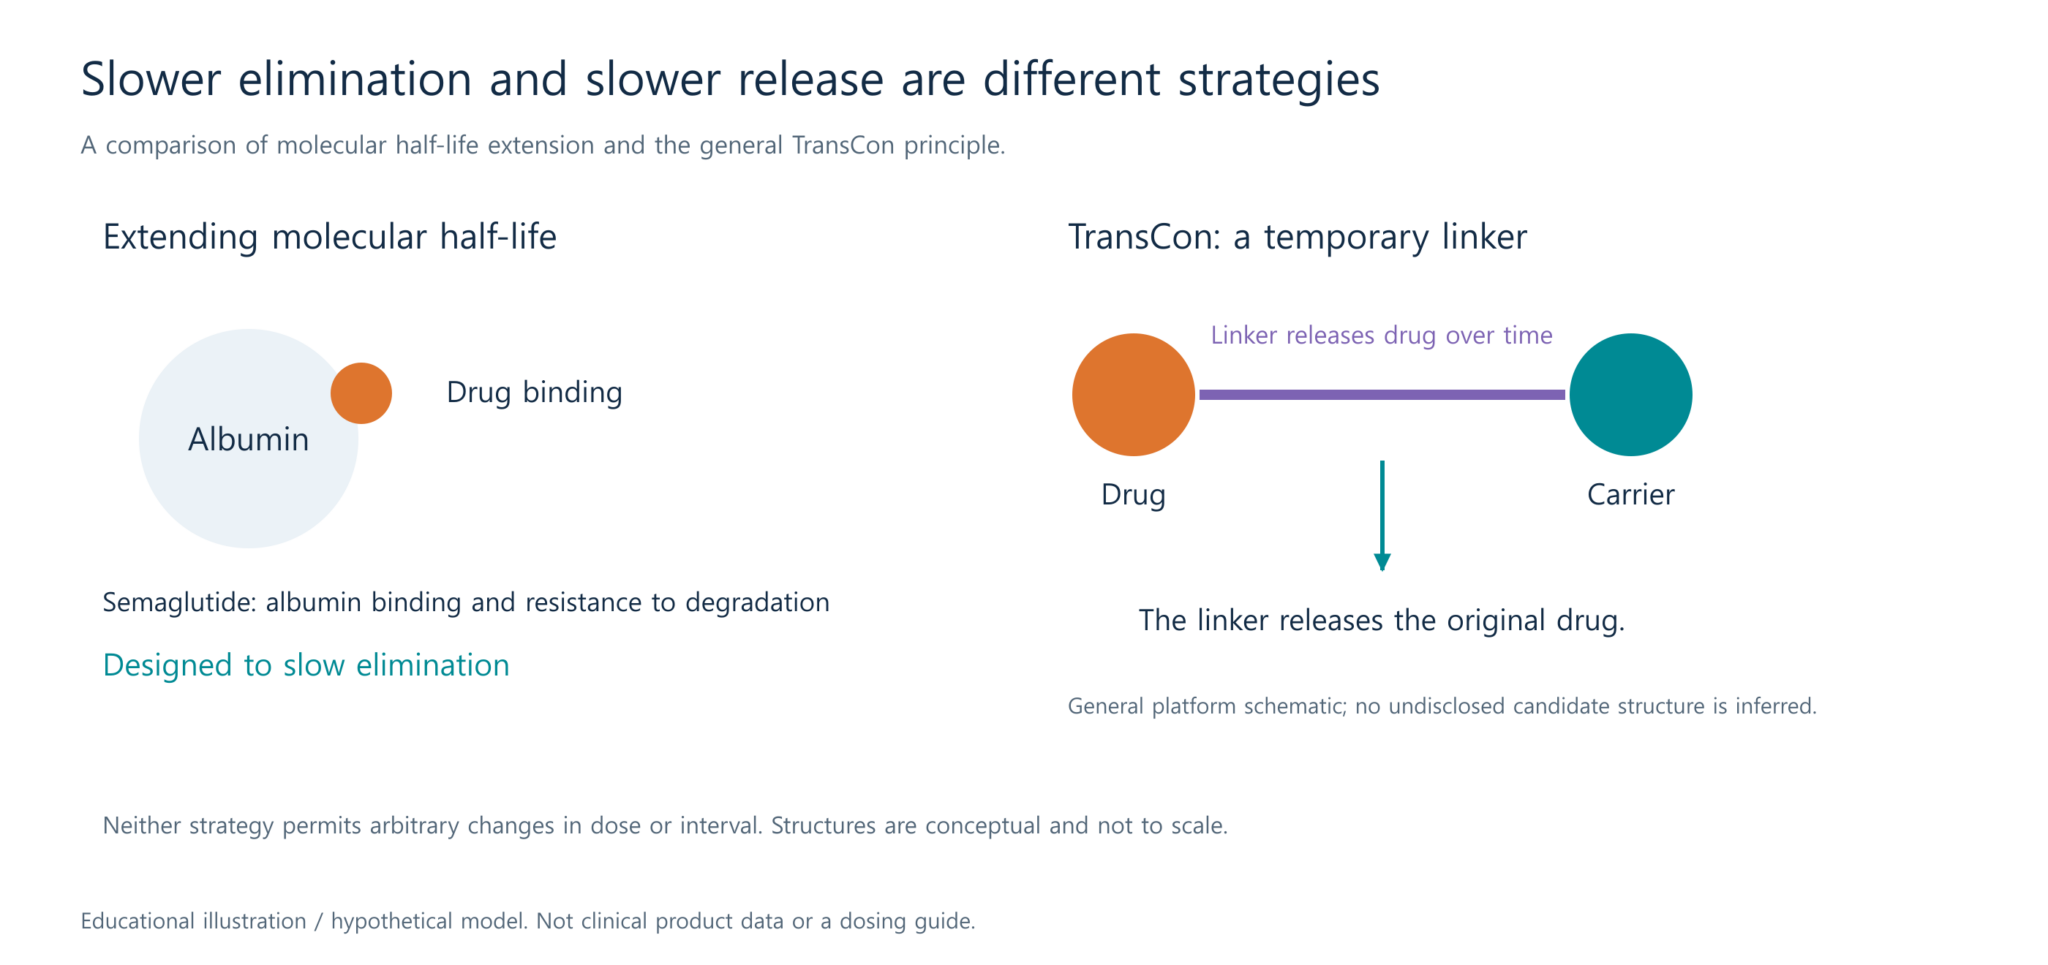
Today’s weekly semaglutide matters here too. Albumin binding and resistance to enzymatic degradation help it persist; its elimination half-life is about one week. Tirzepatide’s is approximately 5–6 days. Drawing weekly Wegovy as a drug released by bursting microspheres would misrepresent how it works. [1, 2]
PK asks how much drug is present, and when
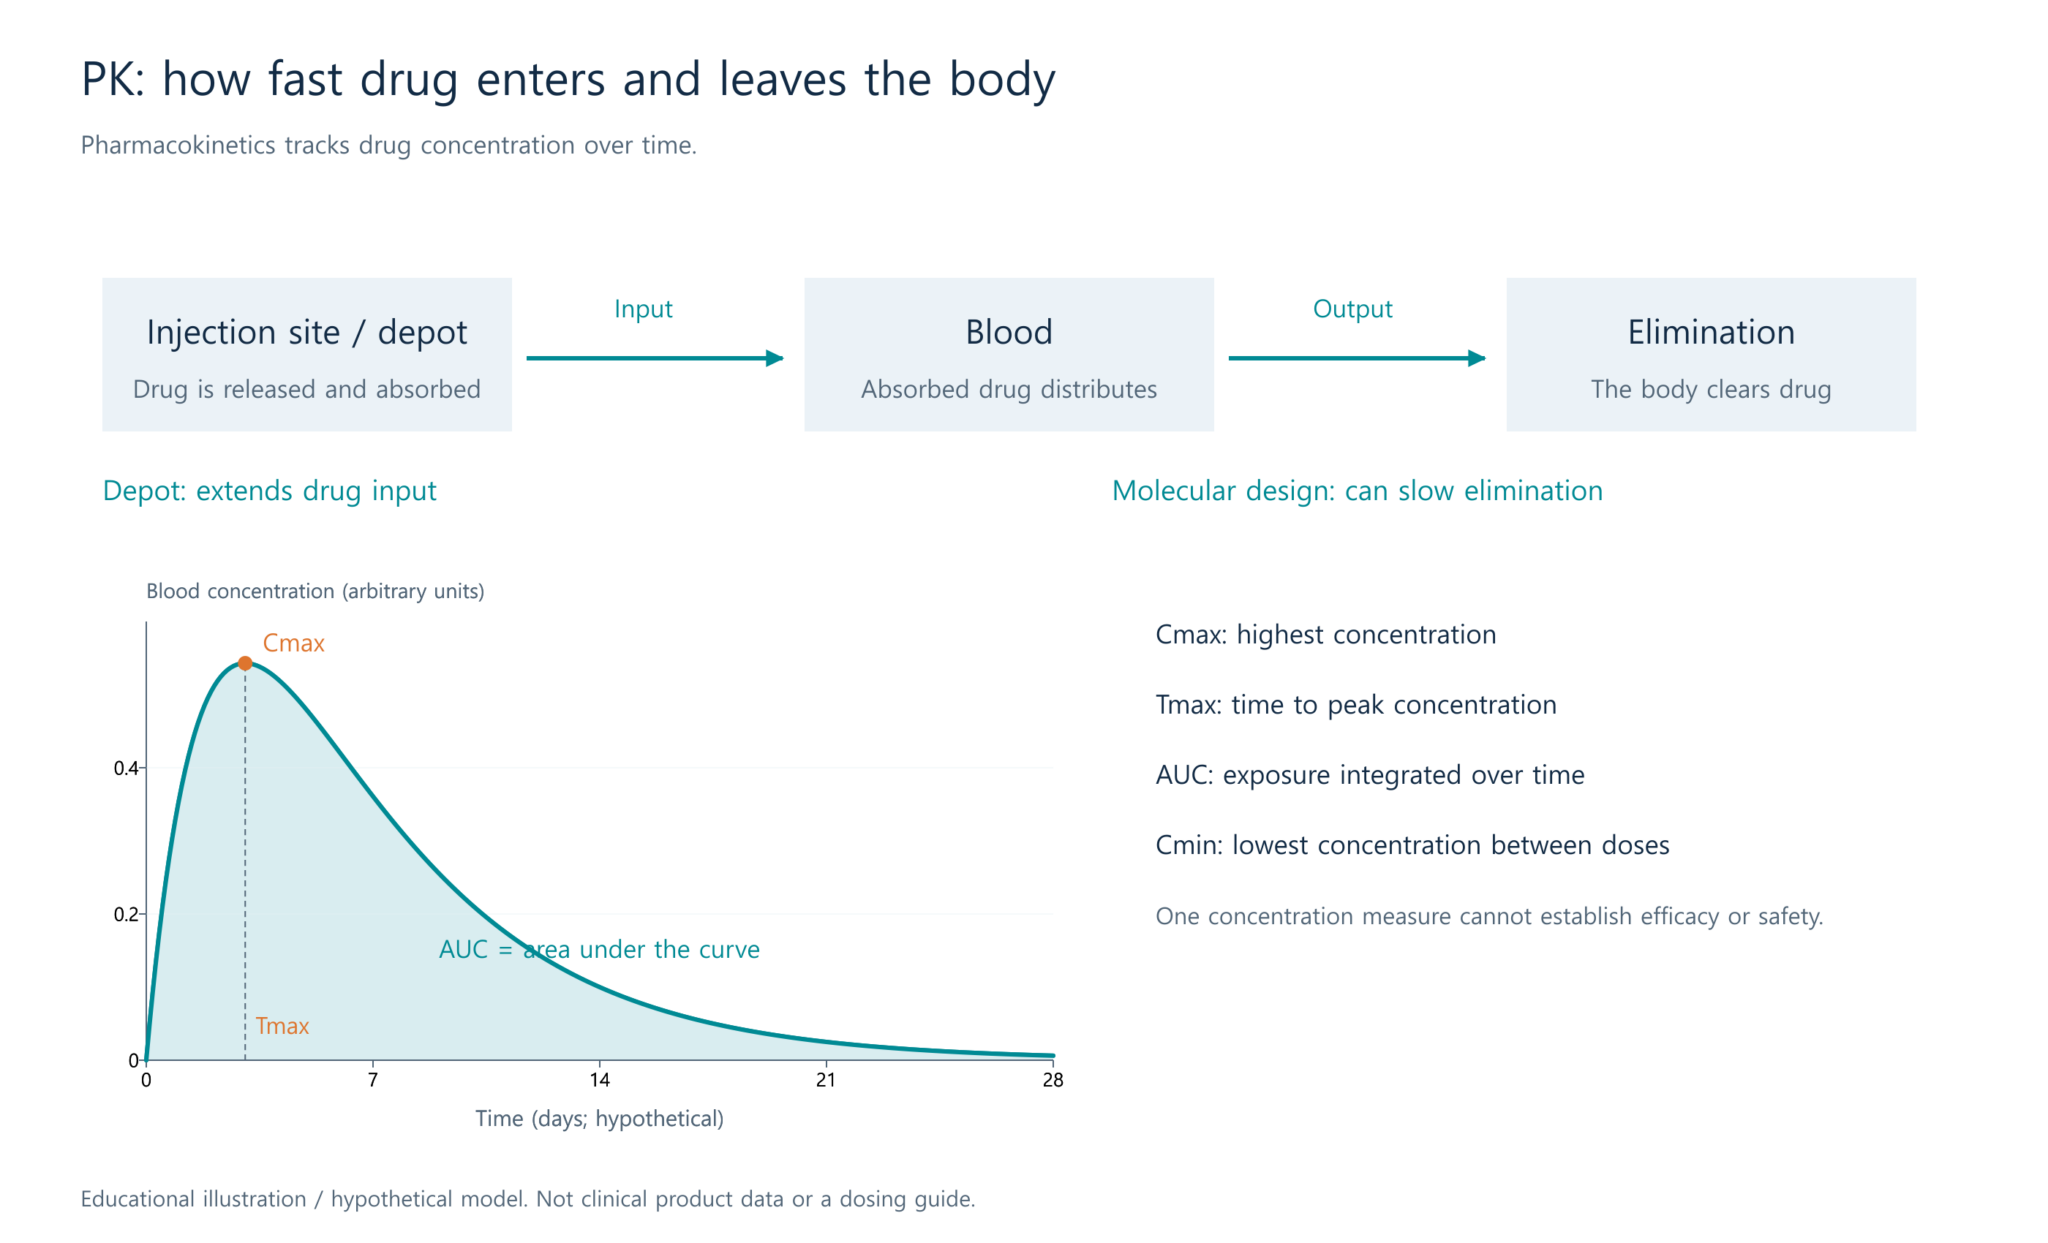
Pharmacokinetics, or PK, describes drug concentration over time. Release and absorption contribute to the input side; elimination removes drug. Drug effect concerns the biological response to that exposure. A concentration graph is therefore not automatically a weight-loss graph. [17]
Peaks, troughs, and total exposure
Cmax is the peak concentration; Tmax is the time to that peak. With repeated dosing, the trough concentration, Cmin, matters too. Look at both the peaks and the valleys. [17]
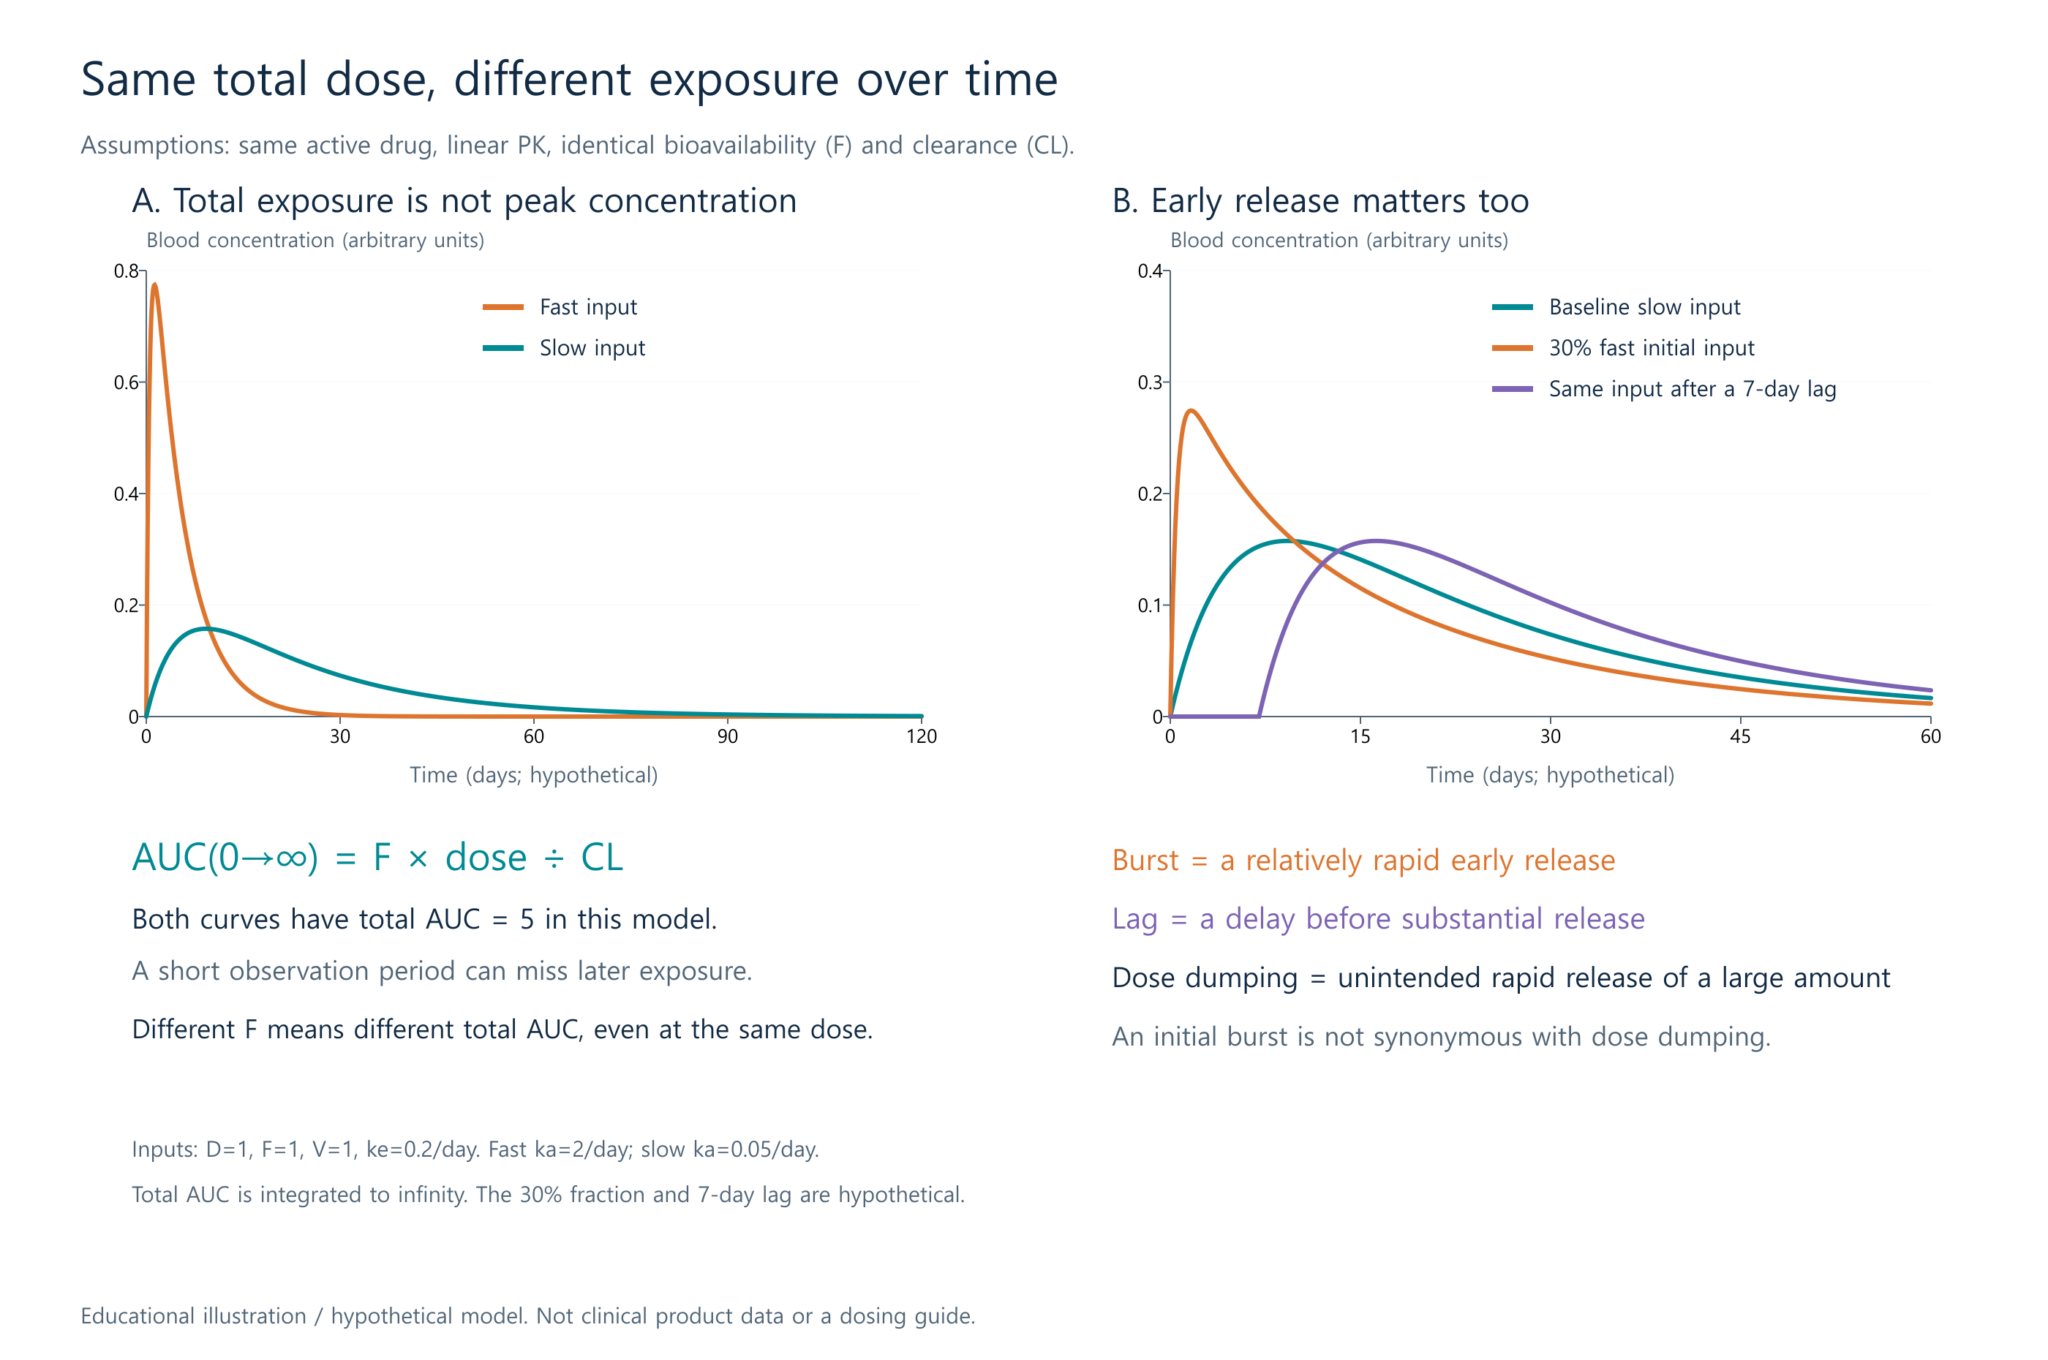
AUC is the area under the concentration curve, a measure of total exposure over time. Equal AUC can come from a brief high concentration or a longer lower one. Equal area alone therefore doesn’t establish equal efficacy or safety. Partial AUC examines exposure during a particular portion of the interval. [17]
A simple equation explains why. Assuming the same active drug, linear PK, and constant clearance, total single-dose AUC = bioavailability × dose ÷ clearance. Bioavailability, F, is the fraction of the administered dose reaching systemic circulation; clearance, CL, describes drug removal capacity. This is a mass-balance relationship under stated assumptions, not a company’s clinical result.
If F, dose, and CL are unchanged, slower delivery can leave the total area measured all the way to the end unchanged while altering the peak, trough, and early exposure. If the formulation changes F, the same dose needn’t produce the same exposure. This doesn’t give us a prescription rule for multiplying a weekly dose into a monthly one. [17]
How much intact drug survives the wait?
API means active pharmaceutical ingredient—the material responsible for the drug’s activity. Don’t assume all API placed under the skin reaches the blood intact. A 2018 original study observed enzymatic breakdown of GLP-1 analogs, including semaglutide, in homogenized subcutaneous tissue from humans, rats, and minipigs. This was an in vitro tissue experiment, not a measurement of the percentage lost from a monthly depot in patients. [32]
Separate the possible losses. Damage during manufacture or storage, chemical changes within a depot, and tissue-enzyme degradation after release but before blood entry are different processes. Research on another peptide, octreotide, found chemical modification inside PLGA; the evidence consulted here was the abstract, and it doesn’t give semaglutide the same loss rate. Intact drug still waiting inside a reservoir isn’t degraded drug. Elimination after blood entry is also different from loss before absorption. [18, 32, 34, 35]
Four doses of semaglutide 2.4 mg QW—every seven days—add up to 9.6 mg. For this example, “monthly” means exactly 28 days. That sum isn’t automatically a clinically equivalent dose given once every 28 days. The FDA label reports 89% absolute bioavailability for the existing subcutaneous injection; the other 11% cannot simply be assigned entirely to degradation under the skin. [31]
With the same active ingredient, constant clearance, and linear PK, matching only average steady-state exposure gives: 28-day dose = 9.6 mg × weekly-formulation F ÷ 28-day-formulation F. Using 89% for weekly F, a monthly F of 89% gives 9.60 mg; hypothetical values of 70% and 50% give 12.21 mg and 17.09 mg. Those monthly values are teaching assumptions, not measurements from a candidate. Matching the average also doesn’t match peaks, troughs, or safety. [17, 31]
The underlying model is average concentration = F × dose ÷ (CL × dosing interval). First-dose AUC over 28 days and repeated-dose steady-state exposure aren’t the same thing. This calculation isn’t a clinical dose-conversion guide.
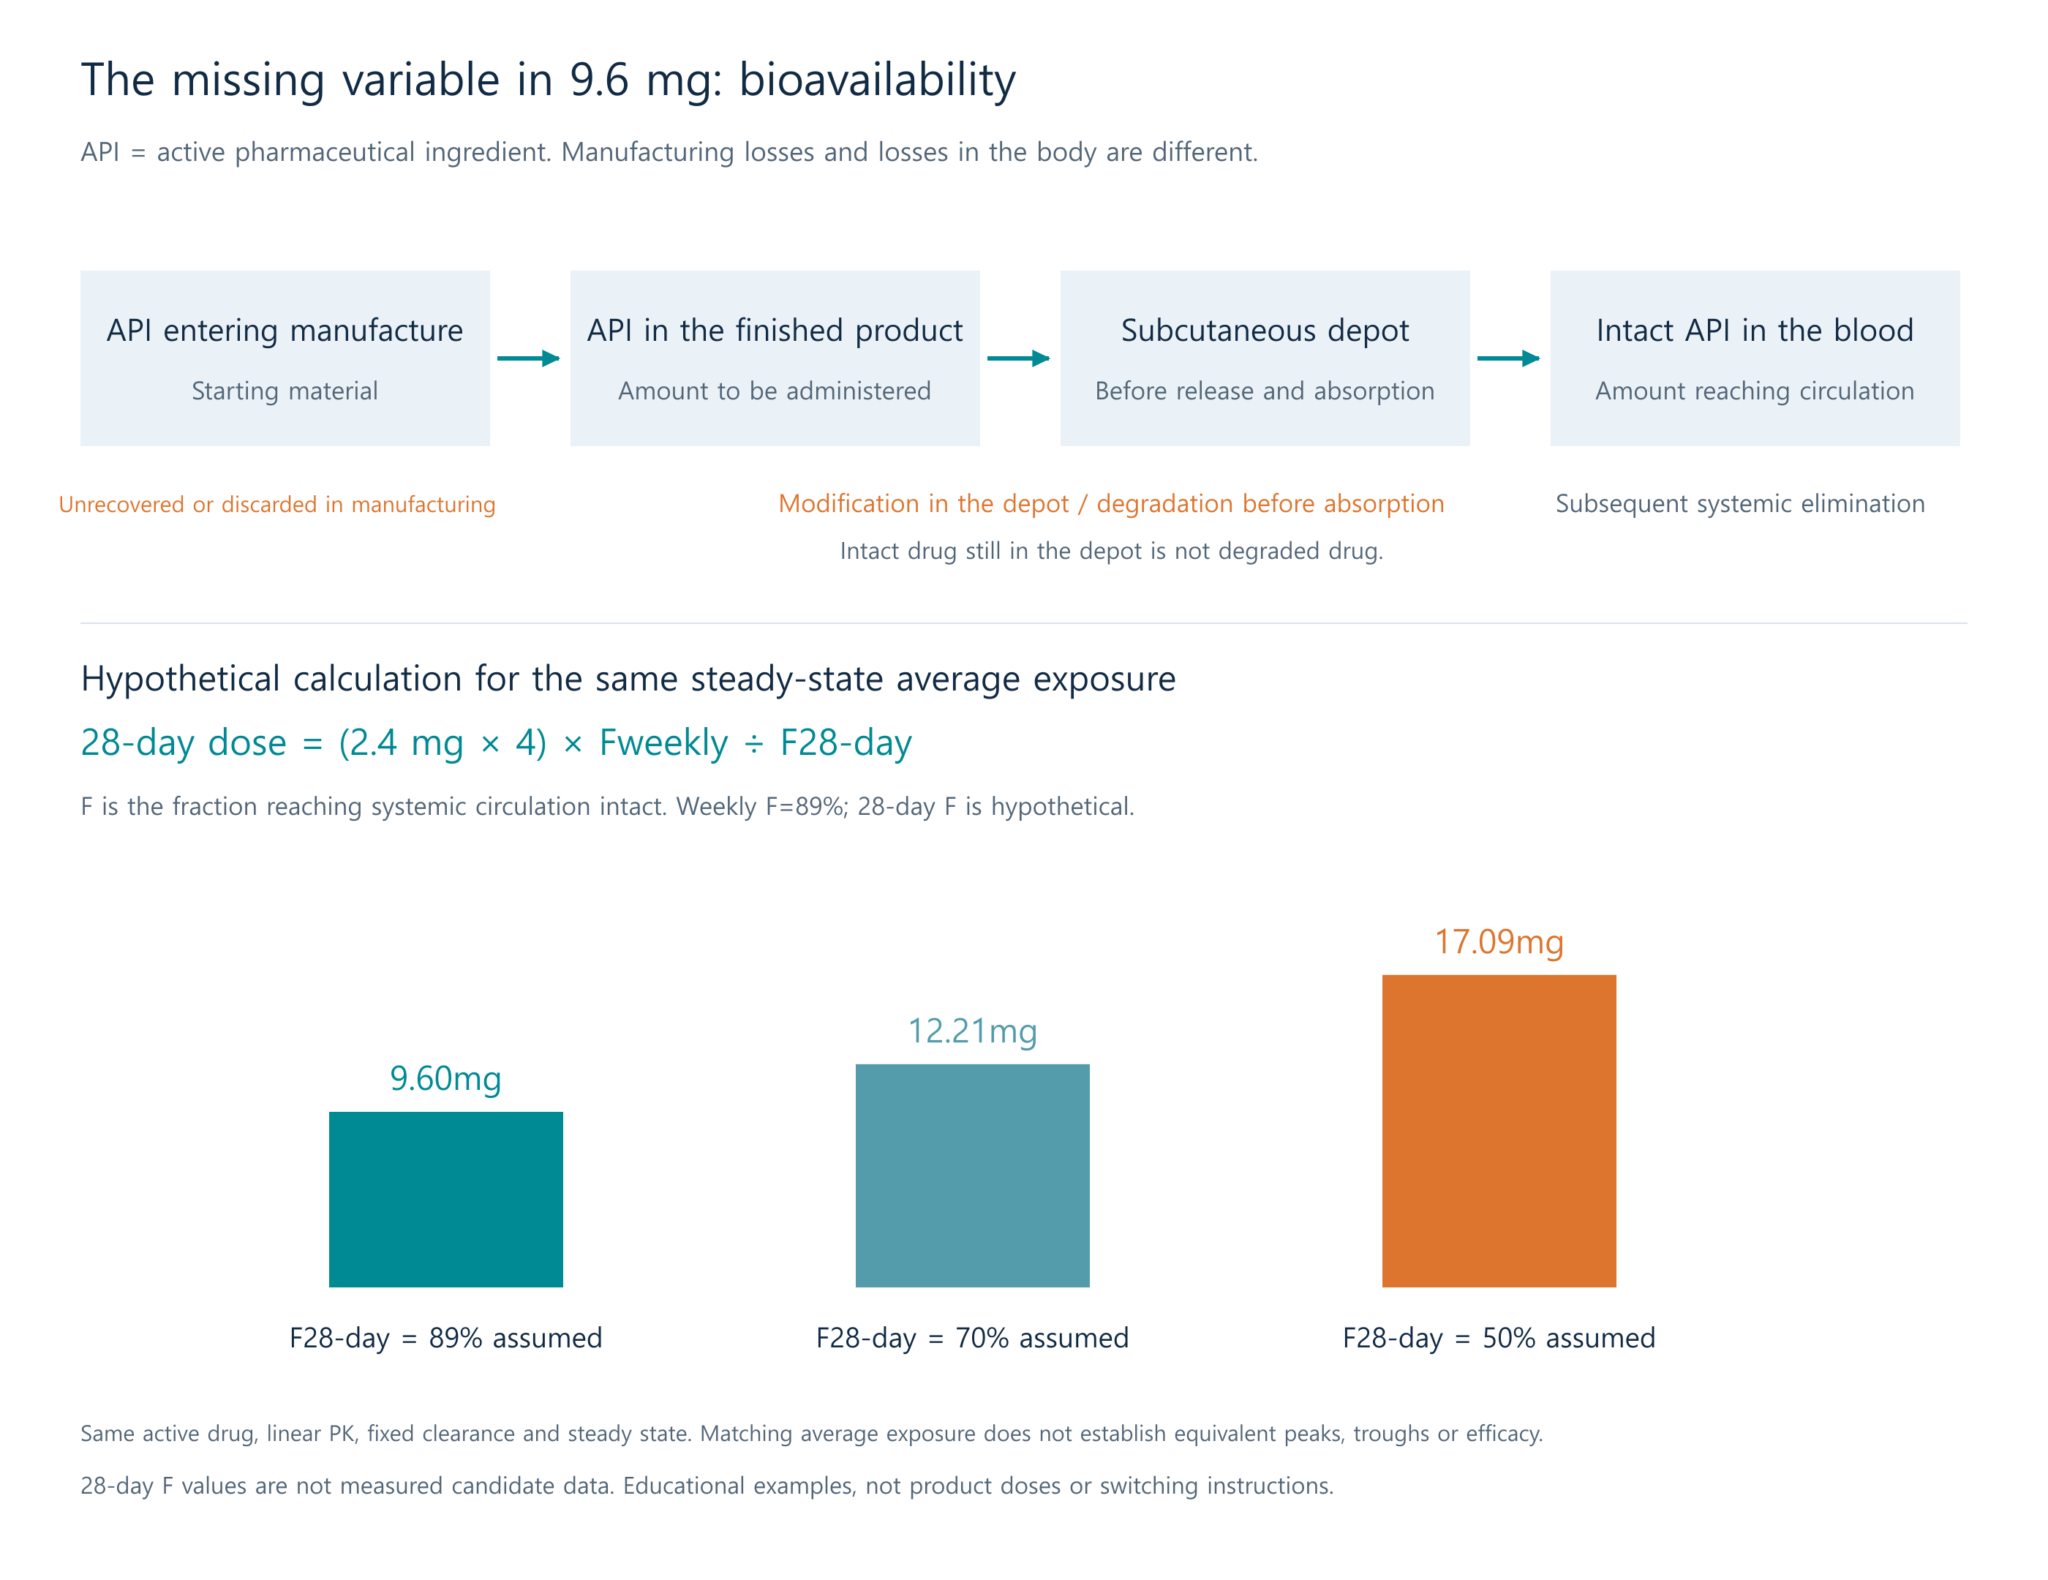
The useful question is how much intact drug reaches the blood from this formulation. Lower monthly F could require more API. But the sources reviewed don’t establish a general rule that every monthly semaglutide formulation must use far more than 9.6 mg. Without degradation, release, and absorption data, we can’t specify the multiplier. [31–33]
CAM2056’s reported similar peak doesn’t establish API efficiency, absolute bioavailability, or equivalent steady-state total exposure. It therefore proves neither that four times the weekly dose is equivalent nor that subcutaneous losses are absent. [33]
Four numbers that should not be mixed up
Four numbers need to stay separate in the cost discussion. Manufacturing recovery and encapsulation efficiency describe how much input material is recovered or incorporated. Drug loading is API’s share of finished-particle mass. Dose is the API mass administered, and F is the fraction reaching systemic circulation intact. High loading may help reduce injection volume, but it doesn’t guarantee high F or low manufacturing cost. [15, 31, 35]
Check each study’s exact denominators for recovery and encapsulation efficiency. Peptide losses can add cost, but total product cost also includes processing time, sterile manufacturing, testing, and rejected material. Without product-level cost data, we can’t rank companies’ economics. [35]
A design using more API needs more specific safety questions. Extra mass isn’t automatically immediate systemic overexposure. Developers need to examine early release, Cmax, AUC, residual exposure, the nature and effects of altered material, and local reactions separately. This doesn’t establish that degradation products are toxic. It means testing what happens if drug added to compensate for expected losses releases differently from expectations. [17, 33, 34]
Burst, lag, and the long tail
Burst describes relatively rapid initial release, lag a delay before substantial release, and tail the exposure that persists afterward. An initial burst isn’t automatically a defect; distinguish it from unintended large-scale release, or dose dumping. The key question is whether the intended schedule is reproducible. [12, 17]
Lowering the peak isn’t always the right objective. Input could become too slow to reach useful exposure promptly, or late exposure could be insufficient. The figures deliberately avoid a universal GLP-1 “efficacy line” or “toxicity line.” Establishing those thresholds would require evidence for the particular drug and regimen. [17]
Half-life can be confusing too. When depot input is slower than elimination, the final decline in concentration can reflect the reservoir’s supply rate more than the molecule’s elimination rate. This is called flip-flop PK. A long tail doesn’t necessarily mean the molecule itself acquired a longer elimination half-life.
Repeated dosing and accumulation
Repeated dosing adds another issue: accumulation. A new dose arrives while some of the previous dose remains, and their contributions overlap. At steady state, the concentration pattern repeats from one dosing interval to the next. It doesn’t mean concentration is constant at every moment. [2, 12, 17]
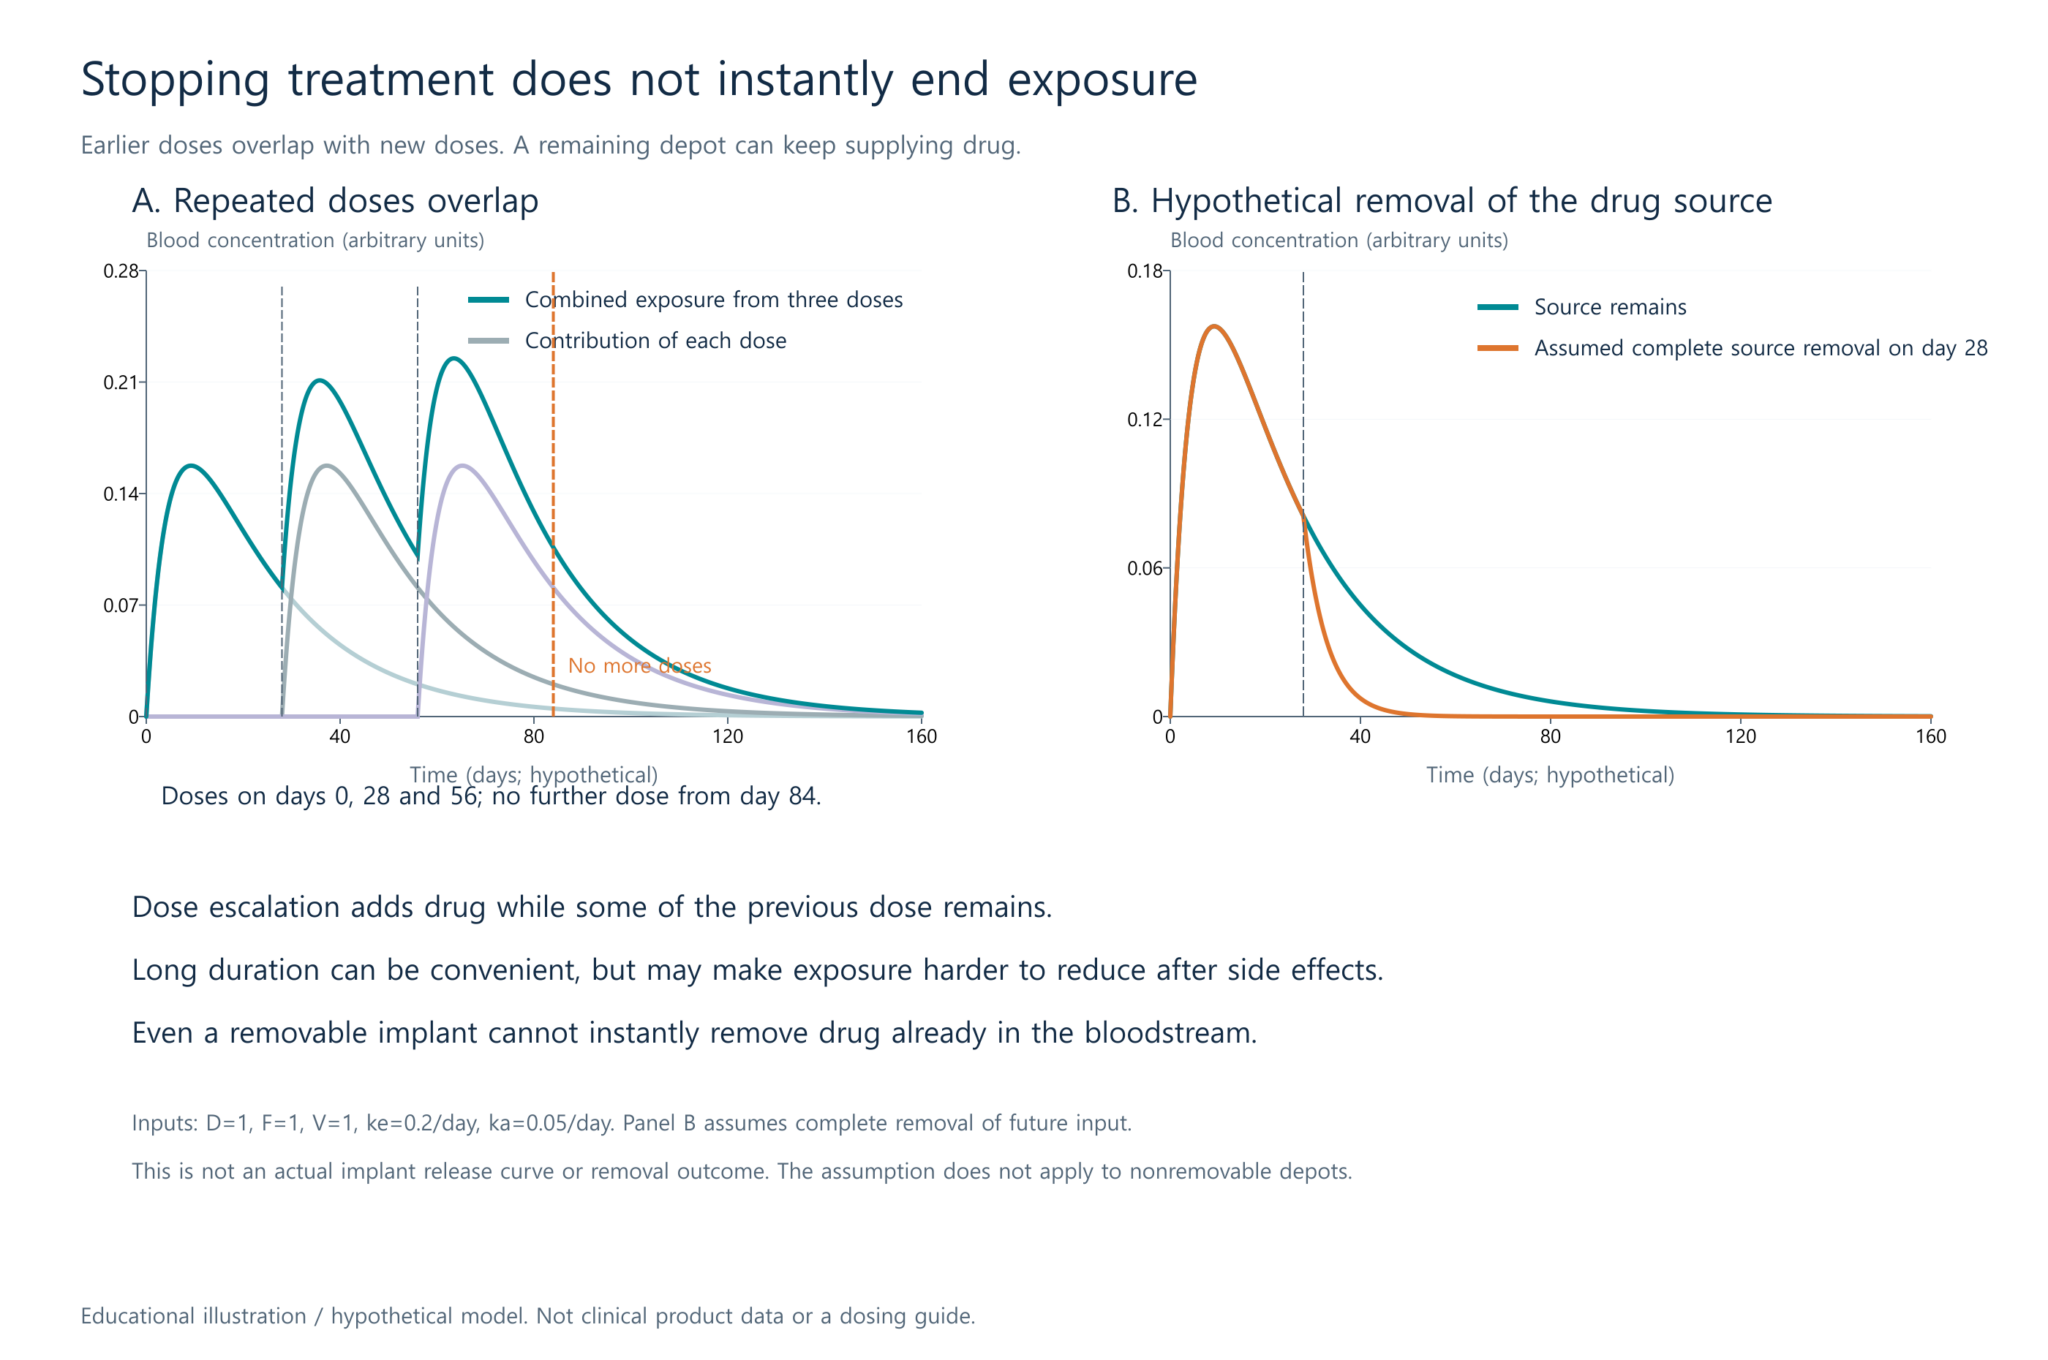
This connects back to titration. A long-lasting supply combines the effects of old and new doses, so initiation, escalation, and stopping need to be evaluated as one timeline. The first injection’s peak can’t establish how manageable the entire treatment course will be. [17, 33, 39]
What removal can and cannot do
Removability also needs a precise reading. Even if removal completely stops further input, it doesn’t take drug already circulating out with it. For a slowly eliminated molecule such as semaglutide, concentration will decline afterward. “Removable” doesn’t mean its effects and side effects instantly disappear. [1, 8]
Is lasting longer enough for approval?
ITCA 650 is a historical counterexample. In August 2024, the FDA issued its final decision refusing approval of the exenatide implant application in its then-current form. Demonstrating safety and a favorable benefit–risk balance was a problem. Review documents also raised device performance, PK variability, manufacturing uniformity, and sterility-assurance issues. [19, 20]
This isn’t a verdict against all implants. It shows that a familiar drug can acquire new uncertainties through its delivery device and manufacturing process. Conversely, a changed device alone doesn’t establish the cause of a particular adverse event. [19, 20]
Moving from a small experiment to a large factory
Think of CMC—chemistry, manufacturing, and controls—as keeping materials, processes, and product quality consistent. Scaling microspheres requires control of mixing, shear, solvent removal, and drying. Changes can affect particle size and distribution, pores, drug distribution, and release. An original exenatide microsphere study found that pressure, temperature, stirring, and flow ratio affected size distribution, encapsulation, initial release, and residual solvent. That’s why batch consistency—getting the same quality from each production batch—matters. [18, 36, 37]
Separate changes to the polymer specification from changes caused by processing. Altering PLGA’s lactide:glycolide ratio, molecular weight, or end groups differs from polymer-chain breakdown during production. Deliberately changing raw-material specifications to preserve performance would create a separate comparability task. A preclinical naltrexone study found morphology and laboratory-release differences after pilot-scale expansion, but no statistically significant difference in in vivo PK. That isn’t proof of equivalence, yet it also shows why scale-up shouldn’t automatically be called failure. [18, 37]
That example involved another drug and preclinical pilot-scale production. It doesn’t establish the same outcome for commercial-scale GLP-1 manufacturing. [37]
ALD scale-up: uniformity is only part of the job
Uniform ALD films and economical mass production of uniform finished medicines are different achievements. Mixing must bring coating gases into contact with the powder; precursor pulses and gas-purging steps affect throughput. A particle-coating scale-up model examines mass transfer, reactor design, and possible improvements. It is a preprint, not a test establishing PharmaShell’s clinical failure or commercial success. The practical question is whether sufficient output and reasonable costs can coexist with coating consistency, drug stability, residue control, and sterile quality. [14, 18, 38]
These questions are more useful than asking which technology lasts longest. The right-hand column below lists evaluation requirements, not defects already demonstrated at particular companies. [1, 8, 12–19]
On a small screen, swipe the table sideways to read every column.
| Approach | How it extends delivery | PK and practical questions |
|---|---|---|
| Microspheres | Diffusion and polymer breakdown release drug | Early burst, lag, tail, and manufacturing reproducibility |
| Lipid depot | Release from a liquid-crystalline gel formed on contact with tissue water | Release and absorption with the actual molecule; repeated-dose concentrations |
| Implant | An inserted reservoir provides ongoing input | Delivery consistency, insertion/removal burden, and exposure remaining after removal |
| ALD | Coating composition, thickness, and dissolution control drug availability | Injection volume at higher doses, human PK, and uniformity at scale |
| TransCon | Temporary linker cleavage releases the parent drug | Candidate-specific release, exposure, and repeated-dose results |
| Existing long-lived molecules | Albumin binding, degradation resistance, and related features | Elimination half-life, concentrations between doses, and escalation design |
Company Guidance and Unconfirmed Timelines
For ALD, separate human observations from modeling. Nanexa’s May 2026 presentation distinguished early clinical proof of concept with liraglutide from semaglutide animal data and simulations of human PK. That isn’t evidence that monthly or quarterly semaglutide has demonstrated weight loss and long-term safety in humans. [21]
Monthly and quarterly administration in the September Novo–Nanexa announcement are development targets. A deal isn’t an approval, launch, or demonstration of the intended interval in patients. Undisclosed candidate-level clinical dates and results remain unknown. [9]
Manufacturing is another milestone to watch. On September 22, Nanexa and Forge Nano announced joint development of large-scale ALD equipment intended to meet good manufacturing practice, or GMP, requirements. Preparing to expand capacity is different from having validated commercial output and quality. [22]
Vivani’s six-to-twelve-month delivery is likewise a design target. Its August 13 update said enrollment and initial dosing of 20 participants were complete in the small, low-dose Australian Phase 1 SLIM-1 study. An early trial doesn’t establish six-month or yearly human dosing. [8]
Vivani projected topline data in November 2026 and Phase 2 in 2027. Camurus guided to starting Phase 2b for its own monthly semaglutide, CAM2056, in the second half of 2026. These are company plans; CAM2056 shouldn’t be conflated with Lilly’s undisclosed collaboration compounds. [8, 27, 28]
Verified Data: The Competition Includes More Than Long-Acting Injections
In US obesity treatment, daily pills compete too. The 2026 FDA label includes oral Wegovy, while Lilly’s Foundayo, orforglipron, was approved on April 1, 2026 for adult weight management. Less frequent injections have to compete with avoiding injections altogether. [1, 23, 24]
Other candidates use different molecular designs. Amgen’s MariTide combines an antibody and peptides to activate GLP-1 receptors and block GIP receptors; Amgen describes its Phase 3 MARITIME program as pursuing monthly treatment. Don’t confuse its GIP blockade with tirzepatide’s GIP activation. [2, 25, 26]
The table covers approaches directly relevant to this discussion and separates approved medicines from candidates. Some recruitment descriptions come from sponsors. Public registry records and all current statuses couldn’t be fully reconciled; this isn’t an exhaustive global competitive landscape. [1, 2, 8, 9, 23–28]
On a small screen, swipe the table sideways to read every column.
| Category and developer | Product and approach | Population and status as of October 1, 2026 | Next evidence to watch |
|---|---|---|---|
| Approved—Novo | Wegovy, GLP-1 | US weight management; FDA labels for weekly injection and daily tablets | An established alternative for new long-acting candidates [1] |
| Approved—Lilly | Zepbound, GIP/GLP-1 | Weekly US injection within its approved indications, including obesity | Benefits of a new formulation relative to the existing product [2] |
| Approved—Lilly | Foundayo, nonpeptide GLP-1 | Daily oral treatment for US adults with obesity or overweight plus a weight-related condition | Convenience and persistence competition [23, 24] |
| Clinical—Amgen | MariTide, antibody–peptide | Phase 3 studies separating populations with and without type 2 diabetes; sponsor lists MARITIME-1/2 as active, not recruiting | Actual trial results and safety; no invented readout date [25, 26] |
| Early clinical—Camurus | CAM2056, lipid depot | Overweight/obesity; listed as Phase 1 in the company pipeline | Whether second-half Phase 2b initiation guidance is achieved [27, 28] |
| Early clinical—Vivani | NPM-139, implant | Australian trial; company reports initial dosing of 20 participants | November data target; longer human evidence remains separate [8] |
| Formulation development—Nanexa/Novo | PharmaShell, ALD | Monthly/quarterly targets; candidate-level phase and recruitment undisclosed | Progress from semaglutide animal/model data to human evidence [9, 21] |
First align the disease, patient population, and treatment duration. Historical diabetes microspheres or pumps aren’t evidence of efficacy for a new obesity drug. Weight-loss percentages from unrelated trials don’t establish superiority, either. Oral and injectable milligram doses also aren’t directly comparable because absorption differs. [1, 12, 19, 25]
Where background reporting ends and interpretation begins
In 2025, BioPharma Dive and MedCity News covered Lilly–Camurus in the context of competition for longer-lasting metabolic treatments. That reporting helps explain the industry’s interest in dosing intervals. It doesn’t establish private motives for terminating a deal or prove which technology wins. [29, 30]
My Insights and Expectations
What I especially want to know is how much extra API a longer interval requires. If a formulation delivers a smaller fraction of intact drug into circulation, it may need more raw material and additional exposure and safety work. I see both manufacturing recovery and intact drug utilization in the body as potential weaknesses in the economics of peptide depots.
For microspheres, I think maintaining batch consistency as the process scales could be a substantial challenge. Raw-polymer specifications and processing-induced changes need separate examination. If developers change those specifications, showing that the resulting formulation performs consistently before and after the change could become an important CMC task.
For ALD, uniform coating alone doesn’t reassure me. I expect substantial hurdles in expanding atomic-layer coating while meeting throughput, cost, and product-quality requirements together. Commercial-scale output, yield, and consistent-quality data would change that assessment. The public evidence doesn’t justify declaring scale-up impossible.
Analysis and Outlook
The evidence suggests that what Novo and Lilly are buying is the option to make treatment easier to continue while managing side effects and titration burden. Weekly drugs can work well and still leave room for less burdensome delivery and product differentiation. That’s an investment interpretation, not an observed improvement in persistence or sales.
There may be no single winning platform. An implant could appeal to someone comfortable with insertion; an injectable depot to someone seeking a longer interval without implantation; a pill to someone avoiding needles. Efficacy, side effects, price, access, and administration burden will all shape the choice. Dosing frequency alone can’t tell us market share.
The positive scenario
The positive scenario is predictable human exposure, tolerable repeat dosing and escalation, and benefits large enough to justify injection or insertion. Add good API utilization, yield, reproducibility, and clinical progress, and a platform company’s deal value could become more tangible. The evidence accumulated matters more than a headline payment ceiling.
The negative scenario
The negative scenario is that prolonged release makes treatment harder to control. Unexpected early exposure, patient variability, accumulation, persistent exposure after stopping, poor API utilization, or manufacturing problems could erode the convenience advantage. If pills and existing weekly products are already convenient and accessible enough, the incremental value of longer intervals could also be smaller.
Stock expectations and regulatory prospects
For stock direction, distinguish the large drugmakers from the platform companies. Human data, retained partnerships, and development progress could raise expectations for a platform company; adverse outcomes could lower them. One delivery technology’s success won’t determine Novo’s or Lilly’s overall stock trajectory. This article hasn’t assessed current share prices or valuations.
The same discipline applies to regulatory prospects. A familiar ingredient or a big-pharma partner can’t simply be converted into an approval probability. ITCA 650 shows why safety, delivery performance, and quality can create separate hurdles. Look at the actual candidate’s clinical and manufacturing evidence, not just the platform name.
Evidence and milestones to watch
The evidence that would change the outlook includes human single- and repeat-dose PK, exposure during escalation and after stopping, patient variability, tolerability, API utilization, yield, reproducibility after scale-up, and practical treatment burden. Nearer-term watch points include Vivani’s projected November data and Camurus’ clinical-start progress. For ALD, watch how monthly and quarterly ambitions translate into human evidence. Timelines are guidance; success is a separate question. [8, 9, 21, 27, 28]
A falling share price doesn’t create an averaging-down thesis merely because the stock is cheaper than before. Reassess whether the core evidence still holds, whether new data reduce risk, the loss that could be tolerated if development fails, and concentration in one platform. Without personal portfolio information, there’s no basis here for specifying a stock or allocation to add.
A useful long-acting drug must do more than keep drug trapped for a long time. It needs to deliver a predictable amount at the right time, with a process that can be managed safely. Novo’s and Lilly’s deals can be read as a search for that possibility. Human concentration curves and clinical and manufacturing outcomes will tell us more about the value created than the size of the deal announcement.
This article explains technologies and public evidence. It isn’t an instruction to change personal treatment or execute an investment trade.
References
- FDA: Wegovy prescribing information, February 2026
- DailyMed: Zepbound prescribing information
- STAY Study: Persistence and adherence with weekly versus daily injectable GLP-1 receptor agonists in US type 2 diabetes care
- Ascendis and Novo Nordisk: TransCon collaboration announcement, November 4, 2024
- Ascendis: Rights to TransCon in metabolic and cardiovascular diseases to revert after termination, September 14, 2026
- Camurus and Lilly: Collaboration and license agreement for long-acting FluidCrystal incretins, June 3, 2025
- Camurus: Expansion of Lilly collaboration, June 1, 2026
- Vivani: Second-quarter 2026 business update, including NPM-139 and the Novo evaluation agreement
- Nanexa: Novo license and collaboration agreement—company release distributed by MFN, September 24, 2026
- Lilly and Amylin: Mutual termination of diabetes alliance, November 8, 2011
- SEC EDGAR: Eli Lilly 2012 Form 10-K
- DailyMed: Bydureon BCise prescribing information
- Camurus: FluidCrystal injection-depot technology
- Nanexa: What is PharmaShell?
- Nanexa: Potential benefits of PharmaShell
- Ascendis: TransCon technology
- FDA: In Vivo Pharmacokinetic Bioequivalence Studies for Long-Acting Injectables—Considerations and Challenges
- FDA: FY2016 Regulatory Science Report—Long-Acting Injectable Formulations
- FDA: ITCA 650 advisory committee briefing document, September 21, 2023
- Federal Register: Final Decision on the Proposal To Refuse To Approve ITCA 650, August 2024
- Nanexa: PharmaShell monthly and quarterly semaglutide presentation, May 19, 2026
- Forge Nano and Nanexa: ALD manufacturing joint development—company release, September 22, 2026
- FDA: Foundayo prescribing information, July 2026
- FDA: Foundayo approval announcement, April 1, 2026
- Amgen: The Story of Maridebart Cafraglutide (MariTide)
- Amgen: MARITIME clinical study program
- Camurus: R&D pipeline
- Camurus: CEO statement for the second quarter of 2026
- BioPharma Dive: Lilly partners with Camurus in search of a long-lasting obesity drug
- MedCity News: Following Novo Nordisk, Eli Lilly Lands Partner for R&D of Longer-Acting Metabolic Meds
- FDA: Wegovy prescribing information—subcutaneous bioavailability, Section 12.3
- Original research: A liquid chromatography high-resolution mass spectrometry in vitro assay to assess metabolism at the injection site of subcutaneously administered therapeutic peptides
- Camurus: CAM2056 Phase 1b topline results, November 10, 2025
- Original research abstract: Effect of inner pH on peptide acylation within PLGA microspheres
- Original research: Efficient aqueous remote loading of peptides in poly(lactic-co-glycolic acid)—full paper archived by the German National Library
- Original research: Injectable sustained-release PLGA microspheres of exenatide prepared by supercritical fluid extraction of emulsion
- Original research: Transitioning from a lab-scale PLGA microparticle formulation to pilot-scale manufacturing
- Preprint: Modeling scale-up of particle coating by atomic layer deposition
- Novo Nordisk: Wegovy US prescribing information, June 2026—initiation and escalation
- Lilly: Zepbound US prescribing information, August 2026—escalation and gastrointestinal adverse reactions
- FDA: Wegovy Clinical Pharmacology Review—exposure, gastrointestinal events, and escalation