As of October 1, 2026 (KST)
Let’s look at why siRNA deals keep coming—and how to choose among the companies. Start with why PCSK9 is relatively accessible and when an early lead in a new target such as ALK7 can create value. Then compare the delivery leaders with the clinical and business conditions facing Silence, Wave, and Vir.
In this article
Verified Data
Small interfering RNA, or siRNA, lowers the messenger RNA (mRNA) that carries instructions for making a particular protein. Inside a cell, its guide strand joins the RNA-induced silencing complex, or RISC, and directs Ago2 to cut the target mRNA. This is different from gene editing that permanently changes DNA itself. [1]
The starting point is getting the drug into the right cells. A delivery tag called GalNAc uses the ASGPR receptor on liver cells. Reducing a protein made in the liver can help address disease in another organ. So a drug described as a heart-disease treatment hasn’t necessarily demonstrated direct delivery into heart cells. [1,11]
Alnylam’s AMVUTTRA (vutrisiran) is a useful example. This siRNA reduces production of transthyretin, or TTR. Its March 2025 US label includes adults with wild-type or hereditary transthyretin amyloid cardiomyopathy (ATTR-CM), with an indication to reduce cardiovascular deaths, cardiovascular hospitalizations, and urgent heart-failure visits. It’s a benchmark for connecting delivery to actual disease-related events. [11]
Getting inside a cell isn’t the end of the job. siRNA trapped in an endosome—a compartment inside the cell—must escape to become active. Original studies show that cellular uptake, changes in endosomal membranes, and release of functional siRNA are distinct steps. [23,24]
We need to separate the evidence, too. Was the drug detected in tissue? Did target mRNA or a related protein decline? Did patients’ function or disease outcomes improve? Those are different questions. A biopsy samples a small piece of tissue; a result at one site doesn’t establish uniform delivery to every cell throughout the body. [27,29,30,22]

Why PCSK9 Is a Good Starting Point for siRNA
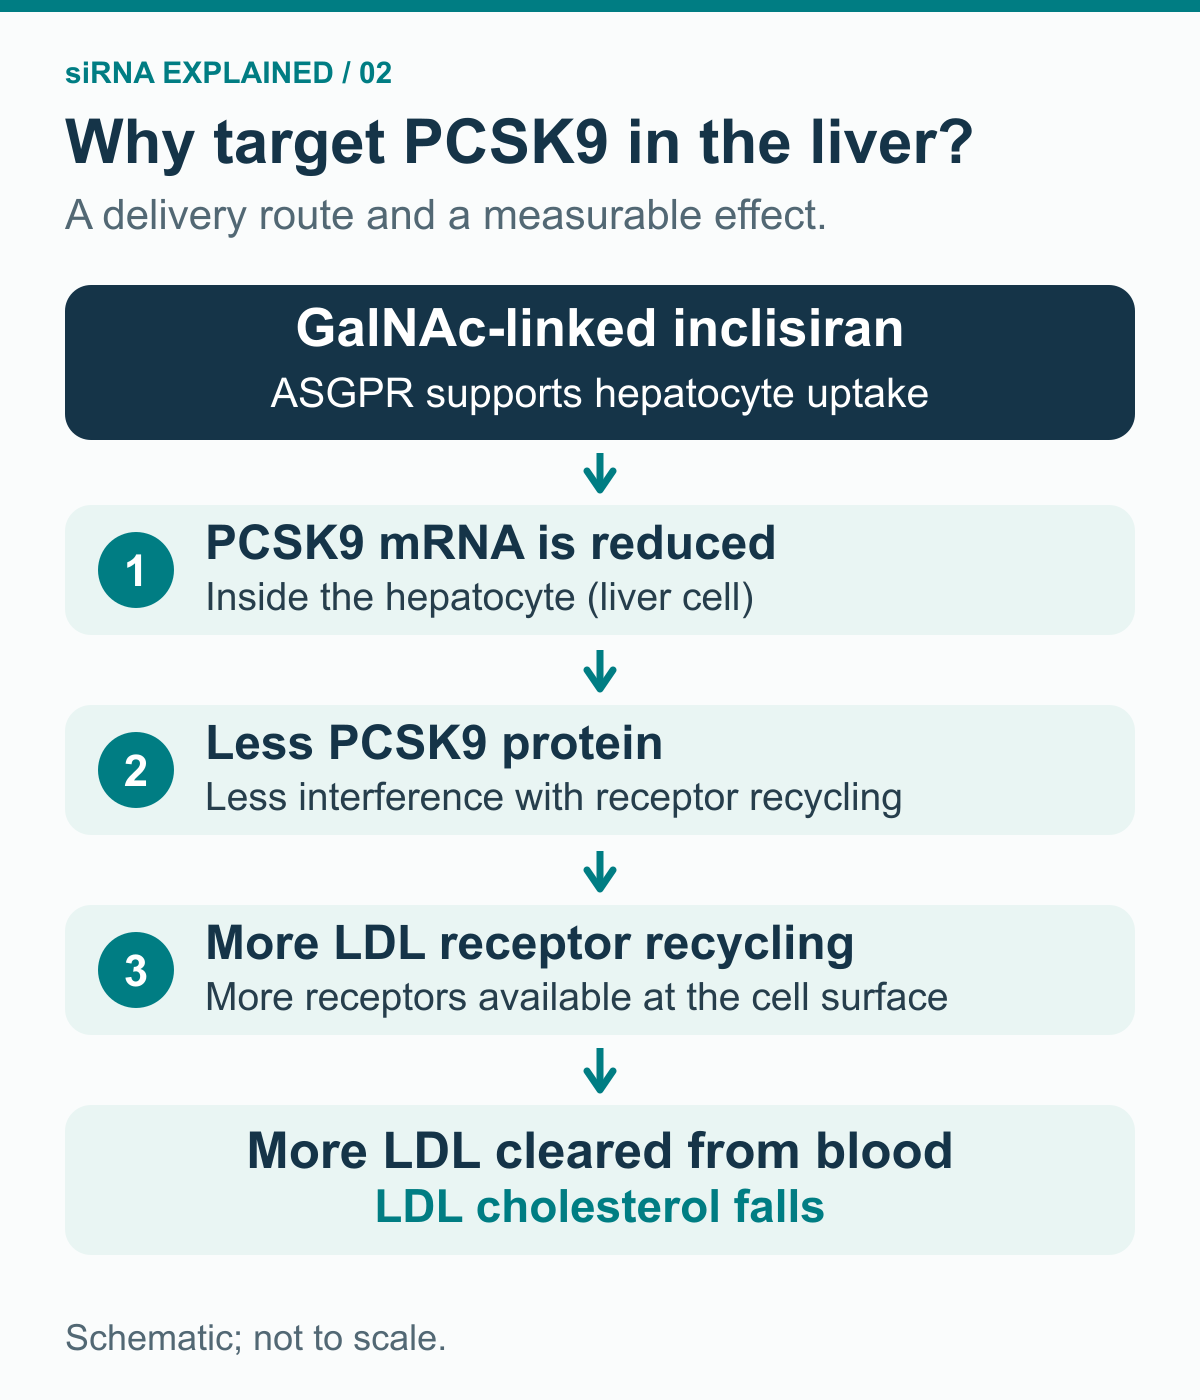
LDL receptors help remove LDL cholesterol from the blood. PCSK9 interferes with those receptors’ recycling. Reducing PCSK9 production in hepatocytes—the liver’s main functional cells—leaves more receptors available to clear LDL. The delivery destination, protein mechanism, and measurable blood marker line up unusually well. [63]
Human genetics provides another starting point. Research involving the Dallas Heart Study linked naturally occurring loss-of-function PCSK9 variants with lower LDL cholesterol. That gives drug developers a reason to try to reproduce part of the biology. It doesn’t mean lifelong genetic variation proves the long-term safety of a drug started in adulthood. [64,65]
Novartis’s LEQVIO (inclisiran) uses GalNAc to reach hepatocytes and reduce PCSK9 mRNA. ASGPR provides a validated route into these cells. That doesn’t make every liver cell easy to reach, and endosomal escape still matters. Liver delivery reduces one source of uncertainty; it doesn’t make drug development easy. [63,1,23,24]
LEQVIO is given initially, again at three months, and then every six months. Its August 2026 US label covers LDL-cholesterol reduction. REPATHA (evolocumab), a PCSK9 antibody, has an indication for reducing major cardiovascular events. Evidence supporting the target and evidence that inclisiran itself prevents those events are different things. [63,66]
Competition already includes statins and injectable antibodies. On July 17, 2026, the FDA also approved Merck’s once-daily oral PCSK9 inhibitor Lipfendra (enlicitide). A new siRNA has to earn its place through treatment burden, access, and price as well as LDL reduction. [63,66,67]
The deals below illustrate the interest in delivery technology. These are selected examples from 2021–2026, not a calculation of industry-wide growth in deal count or value. Amounts are in US dollars and reflect the terms announced at the time. [2,4,5,6,7,8]
| Announcement date | Deal | Technology or assets sought | Upfront cash or acquisition consideration | Amounts to keep separate |
|---|---|---|---|---|
| November 18, 2021 | Novo Nordisk → Dicerna | GalXC RNAi platform and pipeline | Cash acquisition at approximately $3.3 billion in equity value | A company acquisition, not a licensing upfront payment |
| July 24, 2023 | Roche ↔ Alnylam | Hypertension candidate zilebesiran | $310 million upfront | Conditional development, regulatory, and commercial payments |
| November 26, 2024 | Sarepta ↔ Arrowhead | Muscle, central nervous system, and lung programs | $500 million upfront cash | $325 million equity investment; $250 million paid over five years; up to $300 million in near-term milestones; approximately $10 billion in potential future milestones |
| May 14, 2025 | AbbVie ↔ ADARx | siRNA options in neuroscience, immunology, and oncology | $335 million upfront | Additional conditional option fees, milestones, and other payments |
| September 2, 2025 | Novartis ↔ Arrowhead | Preclinical ARO-SNCA and additional targets | $200 million upfront | Up to $2 billion in milestones, plus royalties |
| October 26, 2025 | Novartis → Avidity | Muscle delivery and neuromuscular programs | $12 billion in cash consideration | Company acquisition after separation of early cardiovascular assets |
The Sarepta agreement’s initial $825 million consists of $500 million in cash and a $325 million equity investment. An equity investment gives the investor an ownership stake. Milestones are payments tied to conditions being met. The maximum deal value isn’t cash already in the bank. [5]
The scope of these deals has expanded from liver platforms to hypertension, muscle, and the central nervous system. These examples show interest in broader applications. They don’t establish that every siRNA company becomes more valuable together. [2,4,5,7,8]
Background Reporting
Andrew Marshall also covered dealmaking interest in RNA delivery and manufacturing in a 2025 Nature Biopharma Dealmakers article. The material available here was mainly the public introduction, and the article covers RNA broadly. It isn’t evidence for an industry-wide growth rate specific to siRNA. [20]
Three Groups of Targets to Watch
Let’s divide the target landscape into three groups: hepatic targets with approved products and clinical candidates; newer hepatic metabolic and signaling targets; and targets outside the liver that face direct-delivery barriers. The 23 rows below use US approval status and the cited labels or 2026 company disclosures. Historical validation and an unproven patient benefit shouldn’t receive the same weight.
| Hepatic target | Disease and site of action | Company, asset, and established stage | What investors should distinguish |
|---|---|---|---|
| PCSK9 | Reduces hepatic production to lower blood LDL | Novartis LEQVIO: US approved | Competition from antibodies, statins, and oral enlicitide; LDL lowering versus event prevention [63,66,67] |
| APOC3 | Reduces hepatic production to control triglycerides | Arrowhead REDEMPLO: approved for adults with FCS | Rare familial disease approval versus broader severe hypertriglyceridemia development; Ionis ASO competition [14–17] |
| TTR | Liver-produced protein that deposits in the heart and nerves | Alnylam AMVUTTRA: US approved | Benefit in heart disease doesn’t establish direct heart-cell delivery; competition from stabilizers [11,21] |
| LPA | Hepatic apo(a) production contributes to circulating Lp(a) | Silence zerlasiran: phase 3-ready, seeking a partner; Amgen olpasiran and Lilly lepodisiran: phase 3 | Read alongside pelacarsen’s September cardiovascular-outcomes failure [43–46] |
| AGT | Hepatic angiotensinogen production affects blood-pressure regulation | Alnylam/Roche zilebesiran: in development | KARDIA-3 missed its overall statistical goal; established oral blood-pressure drugs compete [4,13] |
| ANGPTL3 | Hepatic lipid-metabolism protein; homozygous familial hypercholesterolemia (HoFH) | Arrowhead zodasiran: phase 3 YOSEMITE; company announced completed enrollment in July | Regeneron’s antibody EVKEEZA is approved in the same HoFH setting [68,69] |
| TMPRSS6 | Changes hepatic iron regulation to address excess red-cell production in PV | Silence divesiran: phase 2 SANRECO | Phlebotomy and blood-count measures versus thrombosis and survival; not direct bone-marrow delivery [18,40] |
| HAO1 | Hepatic oxalate-production pathway; primary hyperoxaluria type 1 (PH1) | Alnylam OXLUMO (lumasiran): approved | Historical validation of targeting liver production to address kidney disease [70] |
| LDHA | Another hepatic oxalate-producing enzyme; PH1 | Novo Nordisk RIVFLOZA (nedosiran): approved | PH1 in patients age 2 and older with relatively preserved kidney function; not approval for every PH subtype [71] |
| ALAS1 | Hepatic enzyme; acute hepatic porphyria (AHP) | Alnylam GIVLAARI (givosiran): approved in adults | A validated target still requires monitoring for hepatic and renal toxicity [72] |
Next come newer liver targets and pathways. Metabolic dysfunction-associated steatohepatitis (MASH), alcohol-related liver disease (ALD), and inherited protein accumulation all involve the liver. They still have different patient populations and endpoints. Results in one setting can’t simply be carried into another. [73,74,31,75,76]
| New hepatic target or pathway | Disease and approach | Company, asset, and established stage | Competition and remaining tests |
|---|---|---|---|
| INHBE / Activin E | Changes a hepatic signal to affect fat metabolism | Arrowhead ARO-INHBE: phase 1/2a; WVE-007 combination: phase 2a initiated; Alnylam ALN-6222: phase 1 initiated; Silence SLN098: preclinical | Companies pursuing the same target are at different stages; replacement of or combination with GLP-1 drugs requires separate proof [25,51–53,12] |
| PNPLA3 | Fatty liver and MASH, in the context of the I148M genotype | Madrigal MGL-0795, formerly ARO-PNPLA3: monotherapy phase 1 completed | Madrigal holds an exclusive global asset license and is pursuing combination with resmetirom; don’t extend genotype-specific results to all MASH [73,77] |
| HSD17B13 | Enzyme associated with liver disease | GSK gatuzosiran/GSK4532990: ALD phase 2 in its second-quarter 2026 report | Distinguish historical MASH research from current ALD development; not a halt to the entire asset [74] |
| SERPINA1 / mutant Z-AAT | Hepatic accumulation associated with alpha-1 antitrypsin (AAT) deficiency | Takeda/Arrowhead fazirsiran: phase 3 | Reducing toxic liver deposits differs from replacing a lung-protective protein; distinguish US profit sharing from royalties outside the US [31] |
| HBV RNA | Viral RNA in infected hepatocytes, not a single human gene | Vir’s Alnylam-licensed elebsiran plus its antibody tobevibart | Reduces HBsAg needed by HDV; an HBV cure and HDV trial results are different claims [56,57,61] |
| GPR146 | Exploratory hepatic metabolic and lipid regulation | Silence SLN365: preclinical | No demonstrated human pharmacologic effect; don’t value it like a clinical asset [51] |
US competition in MASH already includes the GLP-1 drug WEGOVY and the oral thyroid hormone receptor-beta agonist REZDIFFRA. Their accelerated approvals cover adults with noncirrhotic MASH and moderate-to-advanced fibrosis, consistent with stages F2–F3. A PNPLA3 drug could add value in a specific genetic population or a combination, but that additional value still needs evidence. [75,76,77]
Outside the liver, the question becomes whether the drug reaches the relevant fat cells, diseased muscle, or brain cells. These are research directions and evidence milestones, not a list of established clinical successes. [25–30,22,31,32]
| Extrahepatic target | Tissue and disease | Company, asset, and evidence stage | Boundary of the evidence |
|---|---|---|---|
| ACVR1C / ALK7 | Adipocytes; obesity | Arrowhead ARO-ALK7: phase 1/2a; human adipose-tissue data in January 2026 | Early evidence of direct adipose delivery, not confirmation of sustained weight loss [25,78] |
| APP | CNS; Alzheimer’s-related development | Alnylam mivelsiran: company reported completed phase 2 enrollment in cerebral amyloid angiopathy (CAA) and phase 2 initiation in Down syndrome-associated Alzheimer’s disease (DSAD) | Different patient populations; Alnylam holds global rights; fluid-protein changes differ from cognitive or bleeding benefits [28,29,12] |
| HTT | CNS; Huntington’s disease | Alnylam/Regeneron ALN-HTT02: early clinical development | Molecular changes versus functional benefit; company presentation timing appears below [12,28] |
| MAPT / tau | CNS; early Alzheimer’s disease | Arrowhead ARO-MAPT: phase 1/2a; Alnylam ALN-5288: preclinical data and phase 1 design disclosed | Human results for Arrowhead’s systemic subcutaneous approach remain ahead; distinguish published preclinical blood-brain barrier evidence [32,12] |
| DUX4 | Skeletal muscle; FSHD1 | Sarepta SRP-1001, originating at Arrowhead: phase 1/2a | Drug detection and downstream gene signals in muscle biopsies versus functional benefit [26,27,31] |
| DMPK / toxic RNA | Skeletal muscle; DM1 | Sarepta SRP-1003; Novartis del-desiran failed phase 3 HARBOR | The gap between delivery or mRNA reduction and patient function [22,26,30] |
| RAGE | Lung; inflammatory respiratory development | Arrowhead inhaled ARO-RAGE: phase 2 in its 2026 filing | Historical reductions in lavage-fluid protein don’t establish current respiratory clinical efficacy [33,31] |
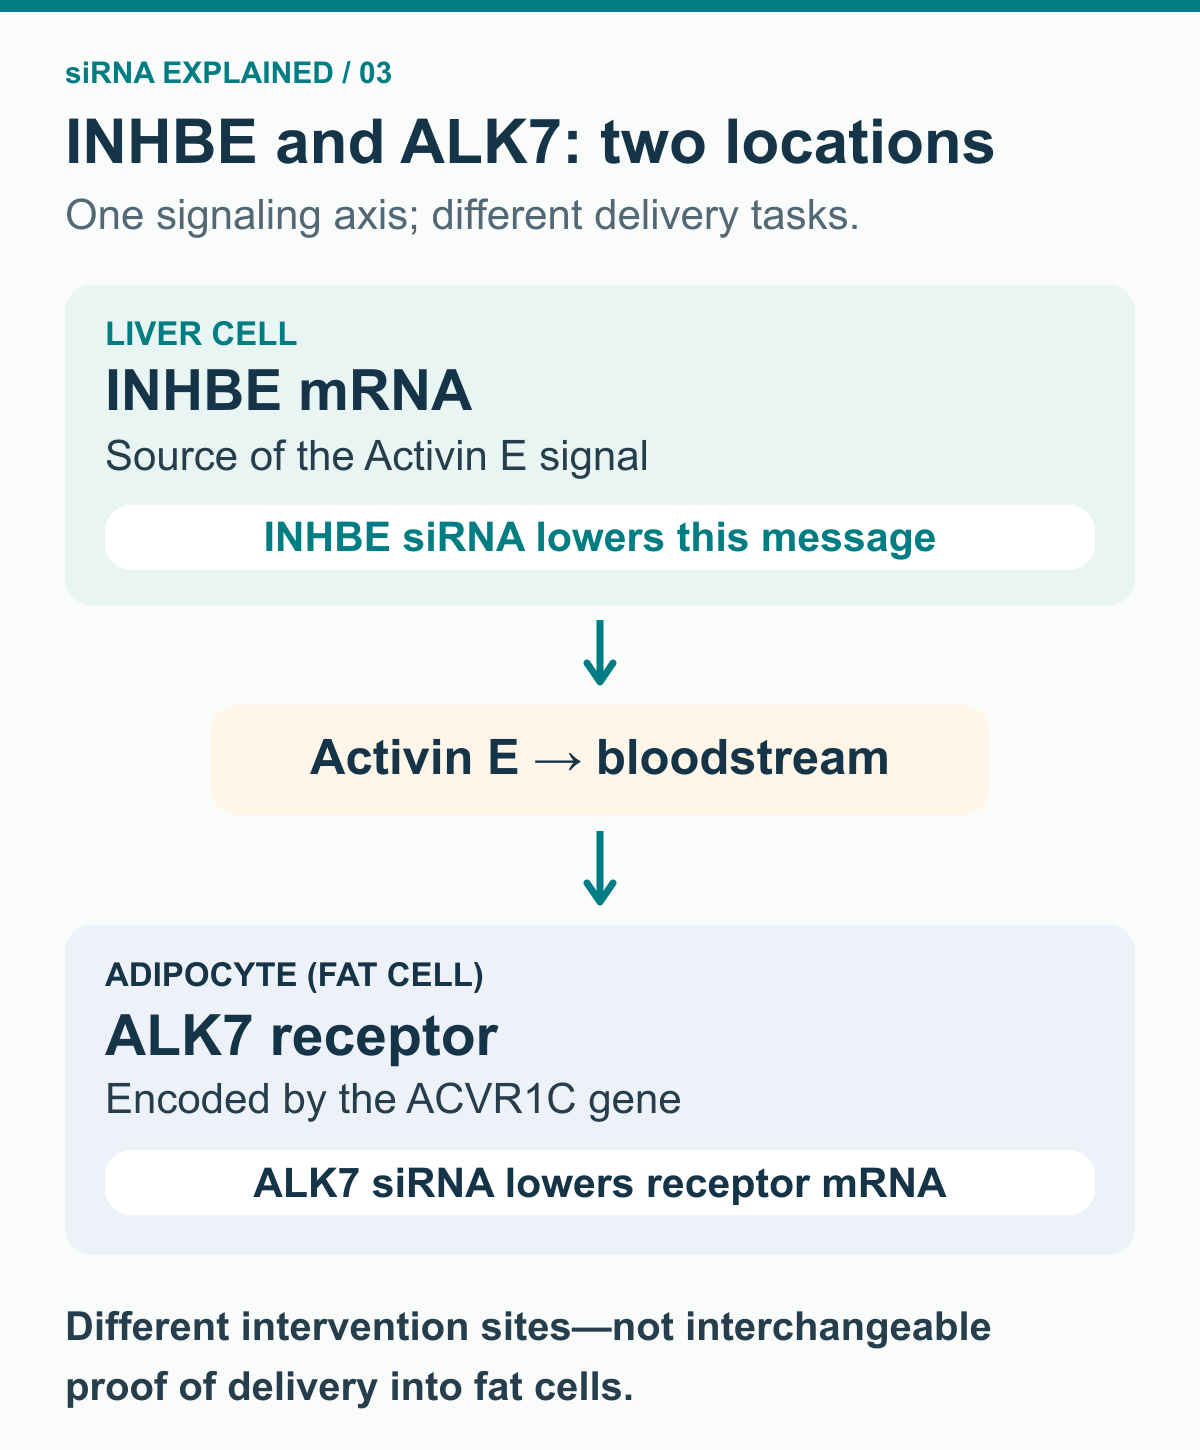
The ALK7 and INHBE distinction matters. ACVR1C encodes ALK7, a receptor on fat cells. INHBE encodes Activin E, a liver-derived signal. They are different nodes in a signaling axis. Arrowhead’s direct ALK7 approach and the hepatic INHBE approaches pursued by Wave, Silence, and Alnylam address related fat biology, but require different delivery evidence. [79,78,12,25,49,51]
Human loss-of-function INHBE variants have been associated with a favorable fat-distribution pattern. That’s a biological rationale, not proof that an INHBE drug produces weight loss, preserves muscle, or remains safe over years. Compare the companies by how much of that gap their human data have closed. [79,78]
How Far Has Delivery Come?
The key comparison is the human evidence in each tissue, rather than the platform name. The table below maps representative technologies and assets. It isn’t an efficacy ranking based on knockdown percentages from different tissues and diseases. Read each row alongside its evidence date and limitations.
| Company and technology | Target tissue and delivery approach | Human evidence | Main unresolved question | Economic rights and investment exposure |
|---|---|---|---|---|
| Arrowhead (ARWR) | TRiM-based approaches for fat, lung, and other tissues; carriers must be distinguished by tissue | ARO-ALK7 adipose-tissue mRNA data, January 2026; lung-lavage protein data after inhaled ARO-RAGE, July 2023 data | Do pharmacologic effects in small samples translate into repeat-dose safety and patient benefit? | Platform developer, but partner rights vary by asset [25,31,33] |
| Alnylam (ALNY) | Liver GalNAc and lipid nanoparticles; C16 conjugates for the central nervous system | Disease-event evidence from approved liver-directed products; early cerebrospinal-fluid protein reductions after intrathecal mivelsiran | Do brain-related biomarkers translate into cognitive or functional improvement? | ALNY holds global rights to mivelsiran; ALN-HTT02 is a Regeneron collaboration [11,28,29] |
| Sarepta (SRPT) | Arrowhead-origin integrin-targeting ligand–siRNA approach for muscle | Drug exposure and downstream gene changes in SRP-1001 muscle biopsies, March 25, 2026 company presentation | Confirmation of repeat-dose performance and functional benefit | Exclusive global licenses to the relevant assets; don’t count the same technology twice across ARWR and SRPT [26,27,31] |
| Novartis (NVS)/Avidity | TfR1 antibody–siRNA conjugates for muscle | Muscle DMPK mRNA reduction in MARINA; subsequent failure on HARBOR’s phase 3 primary endpoint | The gap between molecular effects and functional effects | Acquisition completed in February 2026; exposure is through NVS, not an independent Avidity stock [9,10,30,22] |
| Novartis/DTx | FALCON fatty acid–siRNA approach aimed at peripheral-nerve Schwann cells | Acquisition-era evidence reviewed here is preclinical | Insufficient confirmation of its latest human development stage in 2026 | Acquired by NVS in 2023; not presented as an independently listed investment [35] |
| City/Biogen | City RNAi and Biogen delivery technology; research on systemic CNS administration | No human delivery results for this collaboration in the reviewed material | Will systemic administration produce the intended pharmacologic effect in humans? | City is private; Biogen handles development and commercialization of collaboration programs [34] |
| ADARx/AbbVie | Combining RNA technology with antibody and tissue-delivery capabilities | No extrahepatic human delivery results established by the agreement | Will the collaboration produce candidates and clinical validation? | Licensing option agreement; the upfront payment isn’t proof of clinical success [6,36] |
Start with Arrowhead’s delivery to fat. On January 6, 2026, the company reported interim phase 1/2a data for ARO-ALK7: four adults with obesity in the 200 mg group had an average 88% reduction in adipose-tissue ALK7 mRNA at week eight. That’s closer to the target tissue than a blood-protein measurement. But it’s four people, and the figure wasn’t presented as a placebo-adjusted reduction. [25]
ARO-INHBE targets the liver, while ARO-ALK7 targets fat cells. A drug that affects fat isn’t necessarily delivered directly into it. In the January interim ARO-ALK7 analysis, the company reported no serious adverse events or adverse-event-related discontinuations. A small, early sample doesn’t establish long-term repeat-dose safety or improvements in weight and metabolic disease. [25]
In the lung, there’s inhaled ARO-RAGE. In July 2023 data, Arrowhead reported lower sRAGE protein in human bronchoalveolar lavage fluid—fluid collected by washing part of the lung. That is local fluid-based pharmacologic evidence. It isn’t lung-biopsy mRNA data or recent evidence of clinical benefit in patients. [33]
For muscle, look at Sarepta’s SRP-1001 and SRP-1003 together. The company describes an approach linking siRNA to a ligand that binds αvβ6 integrin. SRP-1001 targets facioscapulohumeral muscular dystrophy type 1 (FSHD1); SRP-1003 targets myotonic dystrophy type 1 (DM1). [26]
Sarepta’s March 25, 2026 presentation reported SRP-1001 concentrations in muscle and changes in a composite of DUX4-regulated downstream genes in MRI-guided biopsies. That composite isn’t a measure of how much DUX4 itself declined or proof of functional improvement. These are early exploratory results, with exclusions including samples below quantification limits. [27]
The same presentation’s safety population included 56 people, including placebo recipients. One serious event of chest discomfort was classified as severe and judged unrelated to the study drug. These were early results disclosed on March 25. The presentation date isn’t a substitute for a data cutoff or confirmation of long-term safety. [27]
For the brain, first distinguish the administration routes. Alnylam uses a lipophilic C16 conjugate for CNS delivery, and early mivelsiran (ALN-APP) trials used intrathecal administration, into the space containing cerebrospinal fluid. That route isn’t evidence that a subcutaneous injection crossed the blood-brain barrier. [28,29]
In an early analysis released by the company, ten patients with early-onset Alzheimer’s disease who received a single 75 mg dose had an average 73.5% reduction from baseline in cerebrospinal-fluid sAPPβ at one month. The 2025 material includes this 2024 interim analysis. It measures an APP-related protein in fluid, not mRNA in a human brain biopsy or improved cognition. [29]
Safety needs its own boundaries. Company data as of May 15, 2025 included procedural pain and headache, plus one fatal acute pancreatitis event judged unrelated to the drug. The company’s assessment that there were no drug-related severe or serious adverse events cannot be turned into “there were no deaths” or a definitive statement about the latest overall safety profile. [29]
Arrowhead’s ARO-MAPT, by contrast, aims to reach the CNS through systemic subcutaneous administration. The blood-brain-barrier penetration evidence cited in its September 29 announcement was preclinical. Human results remain something to evaluate—not an already established human brain-delivery success. [32]
Does Successful Delivery Mean Clinical Success?
Avidity offers an important counterexample. Del-desiran links a TfR1-targeting antibody to a DMPK-targeting siRNA to deliver treatment to muscle. DM1 is a progressive neuromuscular disease that can cause muscle weakness and impaired hand function. [10,22]
The original MARINA publication’s abstract, published in February 2026, reported muscle-biopsy DMPK mRNA reductions in 38 people with DM1. The six patients in the single-dose 1 mg/kg group had a 46% reduction at day 43. In the groups assigned to three-dose regimens, the nine patients receiving 2 mg/kg and 13 receiving 4 mg/kg had reductions of 44% and 37%, respectively, at day 92. The 10 placebo patients had a 0.9% increase. Different dosing schedules and assessment days prevent a simple efficacy ranking by dose. [30]
Safety was the primary endpoint. Two severe, serious adverse events and one participant’s discontinuation were reported. The material reviewed was the paper’s public abstract, which didn’t provide detailed causality assessments for those events. This is why target reduction in tissue and confirmation of patient function need to stay separate. [30]
On September 8, 2026, Novartis subsequently announced that phase 3 HARBOR had not shown statistically significant improvement versus placebo on its prespecified primary endpoint. Earlier target reduction in muscle biopsies didn’t guarantee success on the later functional endpoint. Extending that failure to every muscle-directed siRNA or antibody carrier would also go too far. [22]

Other RNA approaches compete in muscle. Dyne’s DYNE-101 links a TfR1-binding antibody fragment to an antisense oligonucleotide, or ASO. PepGen’s PGN-EDODM1 binds expanded CUG repeats. Both belong in the DM1 competitive picture, but neither should be counted as proof of successful human delivery of DMPK-degrading siRNA. [37,38]
Who Has the Technology—and Who Captures the Value?
Arrowhead and Sarepta can share exposure to the same muscle-delivery risk. An August 2026 filing states that Sarepta holds exclusive global licenses to assets including SRP-1001 and SRP-1003. Arrowhead receives milestones and tiered royalties on net sales, with the upper end described as the low double digits. Arrowhead doesn’t retain the entire product revenue stream. [31]
The same filing shows that Sarepta exercised rights to take over certain clinical-trial responsibilities and that voluntary termination provisions apply before approval. Arrowhead has also raised capital through convertible debt and share issuance. Partner execution, future funding, and dilution remain investment risks alongside delivery performance. [31]
Alnylam’s assets don’t all have the same rights structure either. Its 2025 Form 10-K says it holds global development and commercialization rights to mivelsiran, while ALN-HTT02 is being developed with Regeneron. One platform name doesn’t imply one profit-sharing arrangement across every product. [28]
Arrowhead’s May 2026 PNPLA3 deal is a concrete example. Madrigal obtained an exclusive global license to the asset, now MGL-0795, for $25 million upfront, up to $975 million in conditional milestones, and royalties. That is an asset license—not ownership of every way to target PNPLA3, and not $1 billion already collected. [73,77]
On September 15, Arrowhead also reported early results for ARO-DIMER-PA, which targets PCSK9 and APOC3 together. The company reported protein and lipid reductions. The disclosed detail on analysis populations, time points, and placebo adjustment isn’t sufficient here to rank it across trials or infer cardiovascular-event prevention. [80]
Dicerna ceased independent Nasdaq trading after Novo completed its acquisition in December 2021. Novartis completed the Avidity acquisition in February 2026. Attractive technology and an independently purchasable stock are separate questions. [3,9]
The City/Biogen CNS collaboration and ADARx/AbbVie tissue-delivery collaboration are worth tracking. But the agreements reviewed here don’t establish extrahepatic human delivery success for those programs, and City is private. DTx’s FALCON illustrates another fatty acid–siRNA approach, but the evidence obtained here is limited to its preclinical status at the 2023 acquisition. [34,35,36]
Approved Products and Real Competition Still Matter
A focus on delivery expansion shouldn’t leave out commercialization. Alnylam reported 74% year-over-year growth in second-quarter 2026 product revenue, while cutting its full-year TTR product revenue guidance from $4.4–$4.7 billion to $4.2–$4.5 billion. The company said second-line demand had normalized after an initial period of pent-up demand. [12]
AMVUTTRA is given subcutaneously every three months, with precautions concerning reduced vitamin A levels and supplementation. In the same US ATTR-CM market, the TTR stabilizer acoramidis (ATTRUBY) is approved as a twice-daily oral treatment. Treatment burden matters, but separate trials don’t establish which drug is more effective. [11,21]
Expectations and outcomes also diverged for Alnylam and Roche’s hypertension candidate zilebesiran. In the 2025 KARDIA-3 announcement, the 300 mg group had a placebo-adjusted 5.0 mmHg reduction in office systolic blood pressure at three months, with a nominal p-value of 0.0431. Yet the overall study missed its prespecified statistical-significance criterion after accounting for multiple tests. One p-value below 0.05 doesn’t make the entire trial a success. [13]
Arrowhead has REDEMPLO (plozasiran), approved by the FDA in November 2025. Its indication is as an adjunct to diet to reduce triglycerides in adults with familial chylomicronemia syndrome (FCS), a rare inherited disorder involving impaired triglyceride breakdown. The dose is 25 mg subcutaneously every three months. [14,15]
In August 2026, the company reported that SHASTA-3 and SHASTA-4 randomized a total of 757 people with severe hypertriglyceridemia (sHTG). In the groups receiving 25 mg every three months, median triglycerides at month 12 fell 79% and 81% from baseline, respectively. Those aren’t placebo-adjusted reductions. The company’s topline announcement alone doesn’t let us calculate the absolute size of complication prevention. [16]
This market also includes Ionis’s ASO TRYNGOLZA (olezarsen). Its June 2026 US label includes reducing triglycerides and acute pancreatitis risk in adults with sHTG and triglycerides of at least 500 mg/dL. It’s administered subcutaneously once monthly. REDEMPLO’s dosing interval may be an advantage to investigate, but superiority in efficacy or safety hasn’t been established against that competitor. [17]
Silence: Turning Liver Delivery into Disease Control
Silence Therapeutics (SLN) deserves a closer look as an independent developer. Its mRNAi GOLD platform uses GalNAc to deliver siRNA through ASGPR receptors on liver cells. Having proprietary chemistry and delivering more precisely in humans than Alnylam are different claims. This review didn’t obtain direct comparative evidence supporting the latter. [39]
The central asset is wholly owned divesiran (SLN124). It targets polycythemia vera (PV), a myeloproliferative neoplasm in which too many red blood cells are produced. Phlebotomy removes blood to reduce that burden. Divesiran lowers liver TMPRSS6, increasing the iron-regulating hormone hepcidin and restricting iron available to bone marrow. It addresses a marrow disease without delivering siRNA directly to the marrow. [18,40]
Look at the company’s August 2026 phase 2 SANRECO announcement. In the 36-week double-blind trial, 48 phlebotomy-dependent patients were randomized to 6 mg/kg divesiran every six or 12 weeks, or placebo. The primary endpoint combined absence of phlebotomy and hematocrit below 45% during weeks 18–36. Pooled response rates were 88% for treatment and 19% for placebo (p<0.0001). [18]
Keep the dosing intervals separate. Response rates were 93.8% with six-week dosing and 81.3% with 12-week dosing. Calling this an “88% response with quarterly dosing” would be inaccurate. Silence reported two grade 1 anemia events and transient injection-site reactions, with no new safety findings. Better phlebotomy and blood-count measures in 48 people don’t establish long-term prevention of thrombosis or a survival benefit. The full clinical dataset still matters. [18]
Competition is already here. On August 28, 2026, the FDA approved Takeda’s hepcidin-mimicking peptide Mimrylo (rusfertide) for erythrocytosis in adults with PV. It uses a weekly subcutaneous schedule, with higher doses split into multiple injections. The existing treatment landscape also includes phlebotomy and hydroxyurea, interferon, and ruxolitinib. [19,41]
Another major candidate, zerlasiran (SLN360), targets liver LPA to lower lipoprotein(a), or Lp(a). In the phase 2 ALPACAR-360 trial of 178 people with cardiovascular disease and high Lp(a), the 450 mg every-24-weeks group had a placebo-adjusted, time-averaged reduction of 85.6% through week 36 (95% confidence interval: an 80.3%–90.9% reduction). That’s neither a single-day measurement nor a reduction in heart attacks or strokes. [42,43]
That distinction has become more important. On September 4, Novartis announced that the 8,323-participant phase 3 Lp(a)HORIZON trial lowered Lp(a) but missed the statistical goal for its primary composite cardiovascular-event endpoint. Pelacarsen is an ASO, while zerlasiran is an siRNA; this isn’t a failure of the same drug. It does challenge the assumption that lower Lp(a) automatically delivers fewer clinical events. [44]
Competitors include Amgen, running phase 3 OCEAN(a)-Outcomes with olpasiran, and Lilly, running phase 3 ACCLAIM-Lp(a) with lepodisiran. Silence’s 2026 filing says it is seeking a partner for zerlasiran’s phase 3 development and commercialization. Being ready for phase 3 doesn’t mean phase 3 has started. [43,45,46]
Separate the dates when looking at funding. Silence had $72.054 million in cash and cash equivalents at the end of June. On August 14, it issued 14,907,407 American Depositary Shares and raised approximately $201.3 million before expenses. That added development capacity and diluted existing ownership. Adding the two figures wouldn’t give us cash as of October 1. Nor should first-half spending, affected by items including tax refunds, be mechanically extended into a runway estimate. [43,47]
Partnership history needs filtering too. In March 2026, AstraZeneca notified Silence that it wouldn’t develop SLN312 beyond phase 1. Silence said it expected to regain rights afterward. Past Mallinckrodt and Hansoh programs also have discontinuation or termination histories, so they can’t simply be listed as current backers. Divesiran’s ownership matters, but old partner logos don’t guarantee today’s development funding. [40,43,48,39]
Wave: Changing Fat Signaling Without Delivering Directly to Fat
Wave Life Sciences’ (WVE) WVE-007 is a GalNAc-siRNA using its SpiNA design to target liver INHBE. It aims to lower liver-derived Activin E signaling and influence the ALK7-related pathway in fat cells. A reduction in visceral fat therefore wouldn’t prove direct delivery into those cells. [49]
In the company’s March 2026 announcement, the single-dose 240 mg cohort had 32 participants randomized 3:1 and an average body mass index (BMI) of 32. At six months, placebo-adjusted results were a 14.3% reduction in visceral fat measured by DEXA body-composition scanning (p<0.05), a 5.3% reduction in total fat, a 2.4% increase in lean mass, and a 0.9% reduction in body weight. Visceral-fat loss isn’t weight loss, and increased lean mass isn’t a direct measurement of stronger muscles. [50]
A higher dose didn’t improve every number. At three months, placebo-adjusted changes in the 400 mg cohort were a 5% reduction in visceral fat, a 0.7% reduction in total fat, and a 0.2% decline in lean mass. But that follow-up differs from the 240 mg group’s six months, so a simple dose-failure verdict would be premature. Early company safety data through February 27 showed no serious treatment-emergent adverse events, discontinuations, or deaths through 600 mg. Repeat-dose and long-term safety still need follow-up. [50,49]
On September 23, the company announced initiation of a phase 2a combination trial with tirzepatide. Tirzepatide acts on GIP and GLP-1 receptors and is approved for weight management in the US. Wave therefore needs to show what it could add in combination, as well as what it could offer as an alternative. Arrowhead’s INHBE candidate and its direct fat-cell ALK7 approach are competing paths. Silence’s INHBE candidate SLN098 remains preclinical and shouldn’t be placed at the same stage. [25,51,52,53]
Wave had approximately $490.6 million in cash, cash equivalents, and marketable securities at the end of June. That money isn’t dedicated to WVE-007. WVE-006 and WVE-008 are RNA-editing assets, a different modality from siRNA. Counting all of a multi-technology company’s funding as the value of one siRNA candidate would distort the picture. WVE-007’s detailed contractual economics are another item to examine before investing. [54,55]
Vir: Executing with a Licensed Asset
Vir Biotechnology’s (VIR) elebsiran is a hepatitis B virus (HBV)-targeting siRNA licensed from Alnylam. Hepatitis D virus (HDV) depends on HBV infection. Vir combines elebsiran, which reduces production of the required hepatitis B surface antigen (HBsAg), with its own entry-blocking antibody tobevibart. The investment case centers on the combination’s clinical value more than on a newly invented proprietary delivery platform. [56,57]
Part 3 of the open-label phase 2 SOLSTICE trial randomized 67 participants. Two assigned to antibody monotherapy withdrew before dosing, leaving 32 combination recipients and 33 monotherapy recipients in the treated analysis. The combination used 300 mg tobevibart plus 200 mg elebsiran every four weeks; monotherapy used 300 mg tobevibart every two weeks. Because even the antibody schedules differed, this wasn’t a clean isolation of the effect of adding siRNA. [58]
The original paper’s week-24 primary-endpoint response was numerically lower with the combination: 15 of 32 participants (47%), versus 23 of 33 (70%) with the antibody alone. This composite required HDV RNA below the detection limit or a reduction of at least 2 log10 IU/mL from baseline, together with normalization of the liver enzyme ALT. This small trial used descriptive statistics without prespecified hypothesis testing, so it doesn’t establish statistical inferiority. But we shouldn’t omit that contrary result and tell only a combination-success story. [58]
The company later reported undetectable RNA in 28 of 32 combination recipients (88%) at week 96. That’s a later result with a different definition from the week-24 composite. Potential for sustained viral suppression and confirmed clinical value remain separate. Through week 48 in the original paper, 81% of combination recipients and 94% of monotherapy recipients had an adverse event, most commonly flu-like symptoms and chills. Those aren’t serious-adverse-event rates or proof of superior safety. [59,58]
There’s already a US-approved competitor. On May 22, 2026, the FDA approved Gilead’s Hepcludex (bulevirtide) for adults with chronic HDV without cirrhosis or with compensated cirrhosis. The US regimen is 8.5 mg subcutaneously every day. It received accelerated approval based on RNA and ALT surrogate measures; a benefit on disease-related clinical outcomes hasn’t been established. Vir’s monthly combination raises a treatment-burden question, but efficacy superiority requires direct comparative evidence. [56,57,60]
Rights and funding are separate considerations. Vir bears development costs for the Alnylam-licensed asset and has future conditional milestone obligations. It licensed commercial rights in Europe, Australia, and New Zealand to Norgine. The approximately $1.01 billion in cash, cash equivalents, and investments at the end of June funds the whole company, including oncology. It isn’t all siRNA funding, and Vir doesn’t retain all worldwide sales economics. [61,59,62]
Company Guidance and Unconfirmed Timelines
For delivery expansion, Arrowhead has scheduled its ARO-MAPT phase 1/2a interim-data webinar for October 14 at 11:30 a.m. PDT. Alnylam plans to present initial ALN-HTT02 results at EHDN on October 23 and hold a webinar on October 26. These are dates to assess results, not promises of clinical success or approval. [32,12]
Silence expected to start a phase 3 trial of divesiran every 12 weeks in the first half of 2027. Its filing, based on June cash before the August offering, projected funding into 2028 under its operating plan. That doesn’t confirm that the entire divesiran phase 3 program is funded. Watch the actual phase 3 design and start, the full phase 2 dataset, post-offering spending plans, and a zerlasiran partnership agreement. [18,43]
Wave guided to additional single-dose 600 mg data and initiation of a maintenance trial in the second half of 2026. Separate those planned events from the combination-trial start it has already announced. Its cash-runway guidance extends into the third quarter of 2028, excluding future GSK milestones. That doesn’t guarantee successful follow-up trials or funding for every development expense. [52,55]
Vir expected phase 3 ECLIPSE 1 topline data in the fourth quarter of 2026 and ECLIPSE 2 and 3 results in the first quarter of 2027. ECLIPSE 1 uses deferred treatment as its comparator. ECLIPSE 2 examines switching patients whose response to bulevirtide is inadequate. ECLIPSE 3 is a phase 2b head-to-head comparison with bulevirtide. The questions and populations differ. Vir guided to runway into the second half of 2028. These aren’t fixed readout dates or approval timelines. [56,59]
Arrowhead said on July 27 that YOSEMITE, its phase 3 zodasiran study in 70 people with homozygous familial hypercholesterolemia, had completed enrollment. The company expects study completion in mid-2027, with an LDL endpoint measured over 12 months. That isn’t a promised results or approval date. Silence’s SLN098 and SLN365 remain preclinical, with potential investigational new drug submissions in 2027; they aren’t clinical leaders yet. [68,51]
Here’s how the three developers compare. “Small” here distinguishes their development and business stage from the leading commercial companies; it isn’t a market-cap ranking. Timelines and runway are company guidance. The real investment question is which risks you’re prepared to take. [39,40,18,43,47,49,50,52,55,54,56,61,58,59,62]
| Company | Business thesis being chosen | Current human evidence | Next company-guided catalyst | Capital and rights to examine |
|---|---|---|---|---|
| Silence | Its own liver platform and disease control with divesiran | Phase 2 in 48 people with PV; phlebotomy and blood-count measures | Phase 3 start expected in the first half of 2027; zerlasiran partner unconfirmed | June cash of $72.054 million and August gross offering proceeds of $201.3 million are separate; divesiran is wholly owned |
| Wave | Obesity and body-composition effects through liver signaling | Early, small WVE-007 samples; distinguish weight from fat measures | Additional 600 mg data in the second half of 2026; phase 2a combination-trial start announced | Approximately $490.6 million in June cash and securities supports multiple technologies; detailed economics need further review |
| Vir | Late-stage validation of a licensed siRNA plus its own antibody | Contrary week-24 SOLSTICE composite result alongside subsequent week-96 suppression | ECLIPSE 1 in the fourth quarter of 2026; ECLIPSE 2 and 3 in the first quarter of 2027, as expected by the company | Approximately $1.01 billion at June-end is company-wide funding; Alnylam payment obligations and Norgine regional rights matter |
My Insights and Expectations
Ultimately, the most important factor in this business appears to be how precisely siRNA can be delivered to the target tissue.
My expectation is that companies that establish an early lead in ALK7 or other new targets could have substantial upside potential. This is a hypothesis about the opportunity available to early developers, rather than an established investment outcome.
Analysis and Outlook
Applying that lens, Arrowhead remains the first company to investigate if expanding delivery beyond the liver is the priority. It has different kinds of human evidence in adipose-tissue mRNA, local lung fluid, and partner muscle biopsies. But small samples, repeat dosing, functional benefit, partner rights, and still-unproven systemic human brain delivery all need to be reflected in the price one is willing to pay. [25,27,31,32,33]
Alnylam is the benchmark if proven clinical benefit and commercial maturity matter most. Early CNS pharmacologic evidence adds to disease-event evidence from approved products. Its lower sales guidance and KARDIA-3’s missed statistical goal still matter. Maturity doesn’t mean every pipeline program will succeed. [11,12,13,29]
Among development-stage companies, I would start a deeper investigation with Silence’s divesiran. It brings together asset ownership, clear PV-management measures, a placebo-controlled phase 2 signal, and subsequent financing. The key isn’t calling it “the next Arrowhead.” It’s whether the 12-week regimen holds up in phase 3 and remains competitive on anemia, long-term management, and access. [40,18,19,41,47]
Silence’s upside scenario requires phase 3 replication, a competitive treatment burden, and reasonable development costs and partnership terms. Weaker efficacy, safety problems from iron restriction, insufficient differentiation from an approved competitor, delays, or further dilution would lower that assessment. A major zerlasiran deal or takeover shouldn’t be treated as guaranteed value in the base case. [18,19,41,43,44,45,46,47]
Wave is a candidate for investors willing to assess an early obesity target’s additional potential. Its position could improve if the visceral-fat signal translates, in larger samples, into meaningful weight, metabolic, functional, and durable benefits—and adds value to tirzepatide. If the story remains limited to body-composition changes or the combination adds little, expectations should come down. Today’s evidence isn’t comparable in maturity to that of the leading obesity drugs. [50,49,52,55,53]
Vir is a candidate when the focus is a nearby late-stage clinical test. The question is whether the elebsiran combination delivers sufficient viral suppression, safety, and practicality, more than whether Vir owns an exclusive new carrier. Confirmatory trials need to resolve the different pictures shown by the week-24 composite and week-96 follow-up measures. Failure would call for a fresh valuation. [56,58,57,60,62]
These differences also help explain continued dealmaking. Buyers can be seen as seeking to apply a liver-validated approach to new targets, reach tissues such as muscle and brain, or secure the potential for longer dosing intervals. Deal value still can’t substitute for successful delivery. Acquisitions, technology options, and asset licenses also have different economics. [1,2,4,5,6,7,8,10,11,15,31]
Owning all five companies wouldn’t fully diversify the science. Liver delivery, shared targets, and assets connected through partnerships can overlap. After delivery capability, examine patient benefit, safety, contractual rights, and follow-up trial costs. Approval prospects should be assessed through each product’s confirmatory evidence, rather than assigned to an entire company. [25,30,22,31,39,49,56,61]
For that new-target thesis, Arrowhead’s human adipose-tissue ALK7 evidence and Wave’s early INHBE data and combination program deserve close attention. But Alnylam has already initiated phase 1 for ALN-6222. INHBE isn’t an empty field reserved for small companies. Silence’s SLN098 and SLN365 offer preclinical possibilities, not the same level of confidence as human clinical evidence. [25,51,52,12]
An early lead becomes more valuable if human delivery is followed by meaningful clinical benefit, repeat-dose safety and durability, and economic rights the company retains. The PNPLA3 transaction shows that a new-target asset can attract a real deal. It doesn’t show that competitors are blocked from the target. Without a patent and freedom-to-operate review, it would be wrong to value an early lead as a monopoly. [73,77,12,22,31]
Better delivery can still lead to limited patient benefit or face a more convenient competitor. Oral PCSK9 competition, HARBOR’s failure, and Silence’s terminated partnerships all belong in the downside case. If the share price already assumes success, or substantial dilution comes before proof, a promising target may still make a disappointing stock. [67,22,43]
This isn’t a buy ranking at today’s prices. Share prices, enterprise values, and a personal loss budget haven’t been evaluated, so attractive technology can’t be equated with undervaluation. Before adding to a position, ask whether new evidence reduces the failure case, whether funding reaches the next meaningful test, and whether competition, rights, or the loss you can absorb have changed. The old average purchase price isn’t the starting point.
That leaves ARWR for delivery expansion, ALNY for clinical and business maturity, SLN for a focused clinical thesis around its own asset, WVE for early obesity expansion, and VIR for nearby late-stage validation. Next, watch how brain-delivery data, divesiran’s phase 3 design, WVE-007 follow-up and combination data, and ECLIPSE results change those theses. Choosing a good siRNA company means asking both where the drug goes and what improves after it gets there—and who captures that value. [32,12,18,52,55,56]
This comparison focuses on US approvals, representative delivery technologies, and Silence, Wave, and Vir. It isn’t an exhaustive global review of companies, patents, freedom to operate, or manufacturing costs. Some clinical evidence is limited to company topline announcements or early data. RAGE evidence includes historical pharmacologic measurements; GPR146 remains preclinical. Gaps remain in current recruitment status, complete safety data, and full contractual terms. This is information and conditional analysis, not individualized investment or treatment advice.
References
- Whole-Body Physiologically Based Pharmacokinetic–Pharmacodynamic Modeling for Interspecies Translation and Mechanistic Characterization of Plasma and Tissue Disposition of GalNAc-siRNAs — 2025
- Novo Nordisk to acquire Dicerna Pharmaceuticals including the RNAi research technology platform — 2021-11-18
- Novo Nordisk announces completion of Dicerna Pharmaceuticals acquisition — 2021-12-28
- Roche enters partnership with Alnylam to co-develop and co-commercialise RNAi therapeutic zilebesiran — 2023-07-24
- Arrowhead Pharmaceuticals Announces Global License and Collaboration Agreement with Sarepta Therapeutics for Multiple Clinical and Preclinical Programs — 2024-11-26
- AbbVie and ADARx Pharmaceuticals Announce Collaboration and License Option Agreement to Develop Next-Generation siRNA Therapies Across Multiple Therapeutic Areas — 2025-05-14
- Arrowhead Pharmaceuticals and Novartis Enter into a Global License and Collaboration Agreement — 2025-09-02
- Novartis agrees to acquire Avidity Biosciences an innovator in RNA therapeutics strengthening its late-stage neuroscience pipeline — 2025-10-26
- Novartis successfully completes acquisition of Avidity Biosciences strengthening late-stage neuroscience pipeline and advancing xRNA strategy — 2026-02-27
- Avidity — DM1 disease and pipeline overview
- AMVUTTRA Prescribing Information — 2025-03
- Alnylam — Second-Quarter 2026 Financial Results and Recent Progress (July 30, 2026)
- Roche — KARDIA-3 Results and Phase 3 Development Decision (August 30, 2025)
- FDA approves drug to reduce triglycerides in adults with familial chylomicronemia syndrome — 2025-11-18
- REDEMPLO Prescribing Information — 2025-11
- Arrowhead — Phase 3 SHASTA-3 and SHASTA-4 Results (August 30, 2026)
- TRYNGOLZA Prescribing Information — 2026-06
- Silence — Phase 2 SANRECO Topline Results for Divesiran (August 10, 2026)
- FDA — Approval of Mimrylo for Polycythemia Vera (August 28, 2026)
- Andrew Marshall, Nature Biopharma Dealmakers — Delivering on RNA Therapeutic Deals (2025)
- FDA — ATTRUBY US Prescribing Information (November 2024)
- Novartis provides update on del-desiran Phase III HARBOR study — 2026-09-08
- Image-based analysis of lipid nanoparticle-mediated siRNA delivery, intracellular trafficking and endosomal escape — 2013-06-23
- Imaging small molecule-induced endosomal escape of siRNA — 2020
- Arrowhead Announces Interim Clinical Data on RNAi-based Obesity Candidates — 2026-01-06
- Sarepta Announces First Clinical Data from siRNA Pipeline Targeting FSHD1 and DM1 — 2026-03-25
- Sarepta Clinical Results and Plan Forward: SRP-1001 for FSHD1 / SRP-1003 for DM1 — March 25, 2026
- Alnylam 2025 Form 10-K — 2026-02
- Mivelsiran: Phase 1 Study — 2025-08-05
- An Antibody-Oligonucleotide Conjugate for Myotonic Dystrophy Type 1 — NEJM, February 19, 2026; original abstract in coauthor John Day’s Stanford profile
- Arrowhead Form 10-Q quarter ended June 30 2026 — 2026-08-04
- Arrowhead to Host Webinar with Interim Clinical Data from ARO-MAPT Phase 1/2a — 2026-09-29
- ARO-RAGE: Pre-Clinical and Clinical Overview — not established; data cuts July 2023
- Biogen and City Therapeutics Announce Strategic Research Collaboration — 2025-05-27
- Novartis builds neuroscience pipeline with acquisition of DTx Pharma — 2023-07-17
- AbbVie and ADARx collaboration and license option agreement — 2025-05-14
- Dyne receives FDA Fast Track designation for DYNE-101 — 2025
- PepGen Reports Second Quarter 2026 Results — 2026-08-06
- Silence Form 10-K FY2025 — 2026-03-05
- Silence divesiran EHA2026 follow-up — 2026-06-11
- MIMRYLO US prescribing information — 2026-08
- Zerlasiran—A Small-Interfering RNA Targeting Lipoprotein(a): A Phase 2 Randomized Clinical Trial — 2024-11-18
- Silence Form 10-Q quarter ended June 30 2026 — 2026-08-10
- Novartis Lp(a)HORIZON Phase III topline results — 2026-09-04
- Amgen second-quarter 2026 results — 2026-08
- Lilly Q2 2026 Earnings Slides — 2026-08
- Silence closes upsized public offering — 2026-08-14
- Silence full-year 2023 results and business highlights — 2024-03-13
- INLIGHT Interim Phase 1 Investor Presentation — 2026-03-26
- Wave Form 8-K / INLIGHT March 26 release — 2026-03-26
- Silence second-quarter 2026 financial and business results — 2026-08-10
- Wave initiates WVE-007 tirzepatide combination trial — 2026-09-23
- FDA approves Zepbound for chronic weight management — 2023-11-08
- Wave Form 10-Q June 30 2026 — 2026-07-30
- Wave second-quarter 2026 results — 2026-07-30
- Vir Q2 2026 corporate update — 2026-08-05
- FDA approves first treatment for chronic HDV — 2026-05-22
- Asselah et al. A Phase 2 Trial of Tobevibart plus Elebsiran in Hepatitis D (NEJM original PDF copy hosted by NATAP) — 2025-11-09 online;2026-01-22 print
- Vir second-quarter 2026 earnings release — 2026-08-05
- Gilead FDA accelerated approval of Hepcludex — 2026-05-22
- Vir Form 10-Q June 30 2026 — 2026-08-05
- Vir Fourth Quarter and Full Year 2025 Financial Results — 2026-02-23
- LEQVIO prescribing information — 2026-08
- A spectrum of PCSK9 alleles contributes to plasma levels of low-density lipoprotein cholesterol — 2006
- Teaming with insight — 2018-06-19
- REPATHA prescribing information — 2026-07
- FDA Approves First Oral PCSK9 Inhibitor to Lower LDL Cholesterol in Adults with High Cholesterol — 2026-07-17
- Arrowhead completes enrollment of global phase3 YOSEMITE zodasiran study — 2026-07-27
- EVKEEZA prescribing information — 2025-09
- OXLUMO prescribing information — 2025-04-07
- RIVFLOZA prescribing information — 2025-03
- GIVLAARI prescribing information
- Arrowhead licenses clinical MASH program ARO-PNPLA3 to Madrigal — 2026-05-05
- GSK Q2 2026 pipeline assets and clinical trials report — 2026-07-28
- WEGOVY prescribing information — 2025-08
- REZDIFFRA prescribing information — 2024-03
- Madrigal pipeline
- Activin E is a transforming growth factor beta ligand that signals specifically through activin receptor-like kinase 7 — 2024-04-10
- Rare loss of function variants in the hepatokine gene INHBE protect from abdominal obesity — 2022-07-27
- Arrowhead announces interim topline clinical results for ARO-DIMER-PA — 2026-09-15